

High Blood Pressure in Winter Cold
🩺 Dr. Akram’s Clinical Review & Experience: The Winter Morning Crisis of Marcus Vance
In January of 2021, at precisely 6:42 AM on a Tuesday when the ambient temperature outside my clinic plummeted to -4°C (24°F), Marcus Vance was wheeled through our emergency triage doors. Marcus was 52 years old, weighed 118 kilograms (260 lbs) with a waist circumference of 44 inches, and carried a chronic history of untreated Stage 1 hypertension that he routinely brushed off as “workplace stress.” That morning, he had stepped out onto his snow-covered driveway in thin cotton loungewear to shovel a path for his car. He had taken no more than twelve heavy scoops of wet, dense snow before an invisible vise crushed his chest.
When we strapped the sphygmomanometer cuff to his thick upper arm, the mercury column skyrocketed: 214/118 mmHg. His myocardium was screaming under acute afterload. His coronary arteries, already lined with soft atheromatous plaques from years of visceral adiposity and systemic low-grade inflammation, had snapped shut due to intense peripheral vasoconstriction. His sympathetic nervous system had unloaded an unchecked torrent of norepinephrine directly into his circulation in an emergency effort to conserve core heat. His heart was essentially pumping against a closed hydraulic gate.
We stabilized Marcus that freezing dawn using titrated intravenous labetalol and sublingual nitrates, narrowly dodging a transmural myocardial infarction. But as I sat at his bedside six hours later, watching the fear in his eyes replace the adrenaline, I told him the blunt truth that every clinician with thirty years on the front lines knows: “The freezing air did not create your disease, Marcus; it merely pulled the trigger on a gun loaded by your visceral fat, rigid arterial walls, and metabolic paralysis. If you do not conquer this weight and remodel your vascular tree, next winter will finish what this morning started.”
Marcus listened. We did not hand him a temporary quick-fix; we initiated an aggressive overhaul targeting cold-weather hemodynamics, visceral adipose lipolysis, endothelial nitric oxide preservation, and structured indoor resistance loading. Over the next twelve months, Marcus eliminated 34 kilograms (75 lbs) of metabolically toxic fat, halved his systemic vascular resistance, restored his endothelial elasticity, and brought his resting winter blood pressure down to an unmedicated 118/76 mmHg. His transformation is not an anomaly; it is biological law when you understand how temperature, body mass, and arterial physics interact.
📋 Clinical Index: Table of Contents
🔥 The Wake-Up Call: It’s Time to Transform!
Look down at your body right now. Touch your abdomen. That extra layer of visceral weight is not just passive tissue; it is an active, hormone-disrupting furnace that is choking your microvasculature and forcing your heart to exert hydraulic pressures that crack your vascular lining. Every single winter morning you step into the cold carrying an extra thirty, forty, or fifty pounds, you are rolling the dice with an irreversible coronary event. Stop bargaining with your biology! Your heart has beaten over thirty million times this past year alone under conditions that would grind an industrial engine to dust. It is pleading with you for relief. The cold does not have to be your death sentence; it can become the exact anvil upon which you forge an unbreakable, lean, resilient body. Your transformation cannot wait for the flowers of spring. The work starts right now, in the freezing cold, today!
The Science of Fat Melting: How Your Body Burns Weight Under Hemodynamic Cold Stress
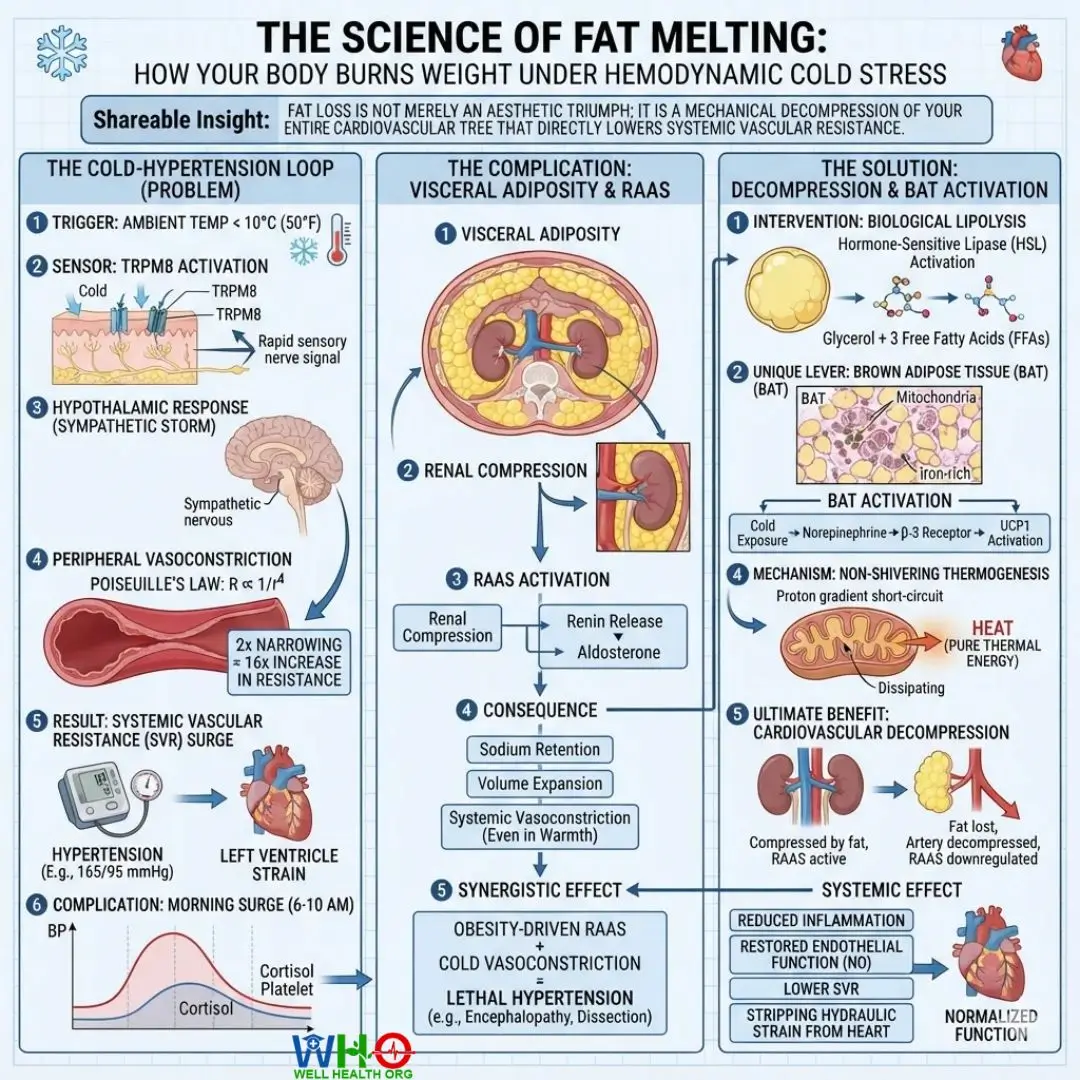
To understand why winter kills more hypertensive individuals than summer, and how melting body fat serves as the ultimate cure for vascular stiffness, we must look at the human body as an integrated thermal-hydraulic system. When ambient air temperatures drop below 10°C (50°F), your body initiates an immediate physiological defense mechanism designed to prevent hypothermia. This survival mechanism is governed by physics: heat flows from high concentration to low concentration. To preserve your core temperature at 37°C (98.6°F), your brain prioritizes the perfusion of your brain, lungs, and liver over your limbs and skin.
Peripheral Vasoconstriction and the TRPM8 Sensor Complex
The primary sensory gateway of cold-induced hypertension is the Transient Receptor Potential Melastatin 8 (TRPM8) ion channel, located predominantly in primary sensory neurons innervating your epidermis. The moment cold air strikes your exposed face, neck, or hands, TRPM8 channels activate, triggering an influx of calcium ions into the nerve terminals. This produces a rapid sensory signal transmitted directly to the thermoregulatory center in the preoptic area of the anterior hypothalamus.
The hypothalamic response is instantaneous. Via the sympathetic efferent nerve fibers, it commands the smooth muscle cells surrounding your peripheral arterioles to contract. This is peripheral vasoconstriction. By dramatically narrowing the lumen diameter of your peripheral microvasculature, your body minimizes blood flow to the skin, converting your dermal tissues into an insulating layer.
However, Poiseuille’s Law of Fluid Dynamics dictates that resistance to fluid flow through a vessel is inversely proportional to the radius of the vessel raised to the fourth power ($R \propto 1/r^4$). If an arteriole constricts to half its normal diameter, the resistance to blood flow within that vessel increases by a staggering sixteen-fold! Because your total blood volume remains unchanged, this vast increase in Systemic Vascular Resistance (SVR) causes mean arterial pressure to surge. Your left ventricle is forced to generate catastrophic contractile pressures simply to push stroke volume out of the aortic valve.
Sympathetic Overdrive, Morning Surges, and Endothelial Failure
Under cold exposure, the adrenal medulla discharges elevated concentrations of the catecholamines epinephrine and norepinephrine. These circulating hormones latch onto alpha-1 adrenergic receptors on vascular smooth muscle, accelerating constriction, while simultaneously binding to beta-1 adrenergic receptors on cardiomyocytes, accelerating heart rate (positive chronotropy) and contractility (positive inotropy).
This cold-induced sympathetic storm peaks during the early morning hours—between 6:00 AM and 10:00 AM. This window overlaps with the body’s natural circadian cortisol release, peak platelet aggregability, and blunted endogenous fibrinolytic activity. If you step outdoors into freezing air during this morning surge, your already-elevated baseline blood pressure can spike by an additional 20 to 40 mmHg within ninety seconds.
Compounding this problem is the cold-induced suppression of Endothelial Nitric Oxide Synthase (eNOS). Nitric oxide (NO) is your blood vessels’ master autocrine relaxant; it signals vascular smooth muscle to relax and dilate. In winter, reduced physical movement, lower ultraviolet-B light exposure, and cold-induced oxidative stress combine to degrade endothelial function. When NO synthesis falters, your blood vessels lose their capacity to buffer the catecholamine surge. They remain frozen in a state of rigid, hyper-reactive constriction.
Visceral Adipose Mobilization vs. Cold Thermogenesis
How does weight loss intervene in this deadly hemodynamic feedback loop? Visceral adiposity—the dense, inflammatory fat wrapped around your mesenteric organs, kidneys, and retroperitoneum—physically compresses your renal arteries. This triggers the Renin-Angiotensin-Aldosterone System (RAAS), causing sodium retention, circulating volume expansion, and systemic vasoconstriction even in warm weather. When you combine obesity-driven RAAS hyperactivation with cold-induced peripheral vasoconstriction, you create a recipe for hypertensive encephalopathy, aortic dissection, or acute pulmonary edema.
Conversely, when you initiate biological lipolysis, you reverse this pathophysiology. Lipolysis is the biochemical breakdown of stored triglycerides into glycerol and three free fatty acids (FFAs). Inside your adipocytes, the hormone Adipose Triglyceride Lipase (ATGL) initiates the cleavage, followed by Hormone-Sensitive Lipase (HSL). When insulin levels are driven down through targeted low-glycemic nutrition and intermittent caloric pacing, HSL becomes hyper-active.
Furthermore, winter offers a unique metabolic lever: Brown Adipose Tissue (BAT) activation. Unlike white adipose tissue (which stores energy and secretes pro-inflammatory cytokines like IL-6 and TNF-alpha), brown fat is packed with iron-rich mitochondria expressing Uncoupling Protein 1 (UCP1). When sympathetic nerves release norepinephrine in response to cold exposure, beta-3 adrenergic receptors on brown adipocytes trigger UCP1 activation. Instead of generating ATP, these mitochondria short-circuit the proton gradient across their inner membrane, dissipating energy entirely as pure heat—a process known as non-shivering thermogenesis.
By actively losing visceral white fat, you decompress your renal vasculature, downregulate RAAS hyperactivity, eliminate systemic circulating inflammatory cytokines, and restore endothelial responsiveness to nitric oxide. Every kilogram of visceral fat lost removes roughly five miles of compressed micro-capillary bed from your vascular circuit, immediately stripping hydraulic strain from your left ventricle.
The Ultimate Fat-Melting Diet Plan (Foods & Fruits)
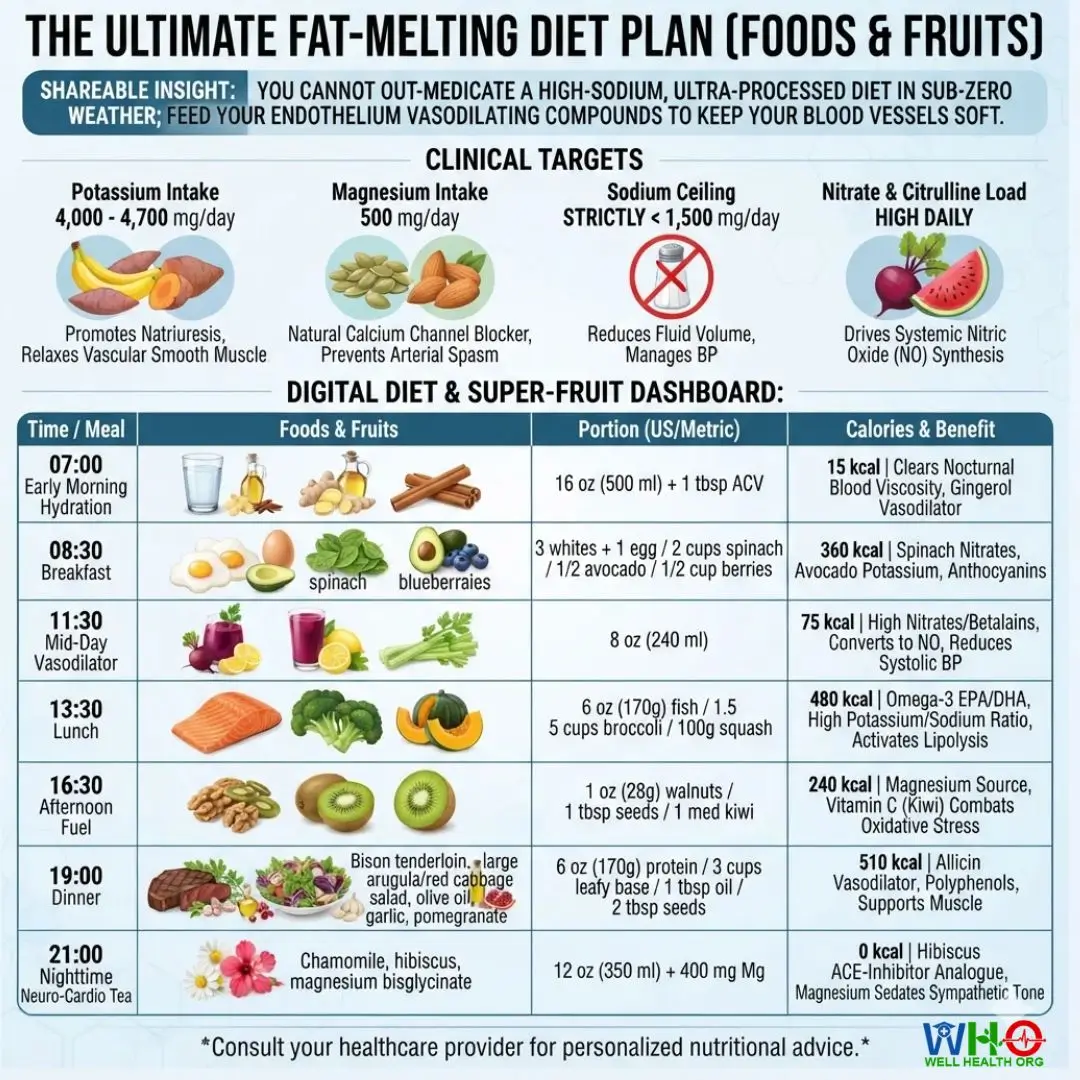
Managing winter hypertension and burning visceral fat simultaneously requires a precise nutritional architecture. In winter, people naturally gravitate toward calorie-dense “comfort foods” that are notoriously high in refined sodium, saturated fats, and processed carbohydrates. This combination is fatal for the hypertensive individual: high sodium expands extracellular fluid volume, while high carbohydrates trigger massive insulin spikes that prevent adipose lipolysis and prompt the renal tubules to reabsorb even more sodium.
The clinical diet protocol below integrates the mineral-balancing prowess of the DASH (Dietary Approaches to Stop Hypertension) paradigm with the anti-inflammatory, mitochondrial-fueling matrix of the Ketogenic-Flex Mediterranean Model. Our targets are absolute:
- Potassium Intake: 4,000 to 4,700 mg/day (to promote natriuresis and relax vascular smooth muscle).
- Magnesium Intake: 500 mg/day (acting as a natural calcium channel blocker to prevent cold-induced arterial spasm).
- Sodium Ceiling: Strictly capped at 1,500 mg/day.
- Nitrate & Citrulline Load: High daily concentrations to drive systemic nitric oxide synthesis through the enterosalivary pathway, bypassing cold-inhibited eNOS.
🥗 Digital Diet & Super-Fruit Dashboard: The Winter Vasoprotective Protocol
| Time / Meal | Foods & Fruits | Portion (US/Metric) | Calories & Benefit |
|---|---|---|---|
| Early Morning Hydration (07:00) | Warm distilled water, raw apple cider vinegar, crushed ginger root, Ceylon cinnamon. | 16 oz (500 ml) + 1 tbsp ACV | 15 kcal | Clears nocturnal blood viscosity; gingerol promotes vasodilation; prevents morning hematocrit spike. |
| Breakfast (08:30) | Pasture-raised egg whites with 1 whole egg, wilted baby spinach, Haas avocado, and wild blueberries. | 3 whites + 1 egg / 2 cups spinach / 1/2 avocado / 1/2 cup (75g) berries | 360 kcal | Spinach delivers inorganic nitrates; avocado provides potassium & monounsaturated fats; anthocyanins improve capillary flexibility. |
| Mid-Day Vasodilator (11:30) | Raw cold-pressed beetroot extract elixir mixed with freshly squeezed lemon juice and celery stalk infusion. | 8 oz (240 ml) | 75 kcal | Heavy dietary betalains and nitrates convert into endogenous nitric oxide via oral microbiome, reducing systolic BP by 6–10 mmHg. |
| Lunch (13:30) | Pan-seared wild Alaskan salmon, steamed broccoli florets, and baked kabocha squash or sweet potato. | 6 oz (170g) fish / 1.5 cups broccoli / 100g squash | 480 kcal | Rich in Omega-3 EPA/DHA to combat cold-induced platelet aggregation; high potassium-to-sodium ratio; activates white-fat lipolysis. |
| Afternoon Fuel (16:30) | Raw unroasted walnuts, roasted unsalted pumpkin seeds (pepitas), and fresh kiwi slices. | 1 oz (28g) walnuts / 1 tbsp seeds / 1 medium kiwi | 240 kcal | Massive magnesium source; kiwi provides bioactive ascorbic acid to combat endothelial oxidative stress; sustained non-insulinogenic fuel. |
| Dinner (19:00) | Grass-fed lean bison tenderloin or grilled organic tofu, large raw arugula and red cabbage salad with extra virgin olive oil, garlic, and pomegranate arils. | 6 oz (170g) protein / 3 cups leafy base / 1 tbsp olive oil / 2 tbsp pomegranate | 510 kcal | Allicin from crushed raw garlic relaxes vascular smooth muscle; high polyphenols inhibit LDL oxidation; supports overnight muscle preservation. |
| Nighttime Neuro-Cardio Tea (21:00) | Chamomile, organic hibiscus flower infusion, and powdered magnesium bisglycinate. | 12 oz (350 ml) + 400 mg Mg | 0 kcal | Hibiscus acts as an organic ACE-inhibitor analogue in clinical trials; magnesium sedates sympathetic nervous tone; promotes restorative slow-wave sleep. |
7-Day Digital Workout & Exercise Plan for Winter Cardiovascular Defense
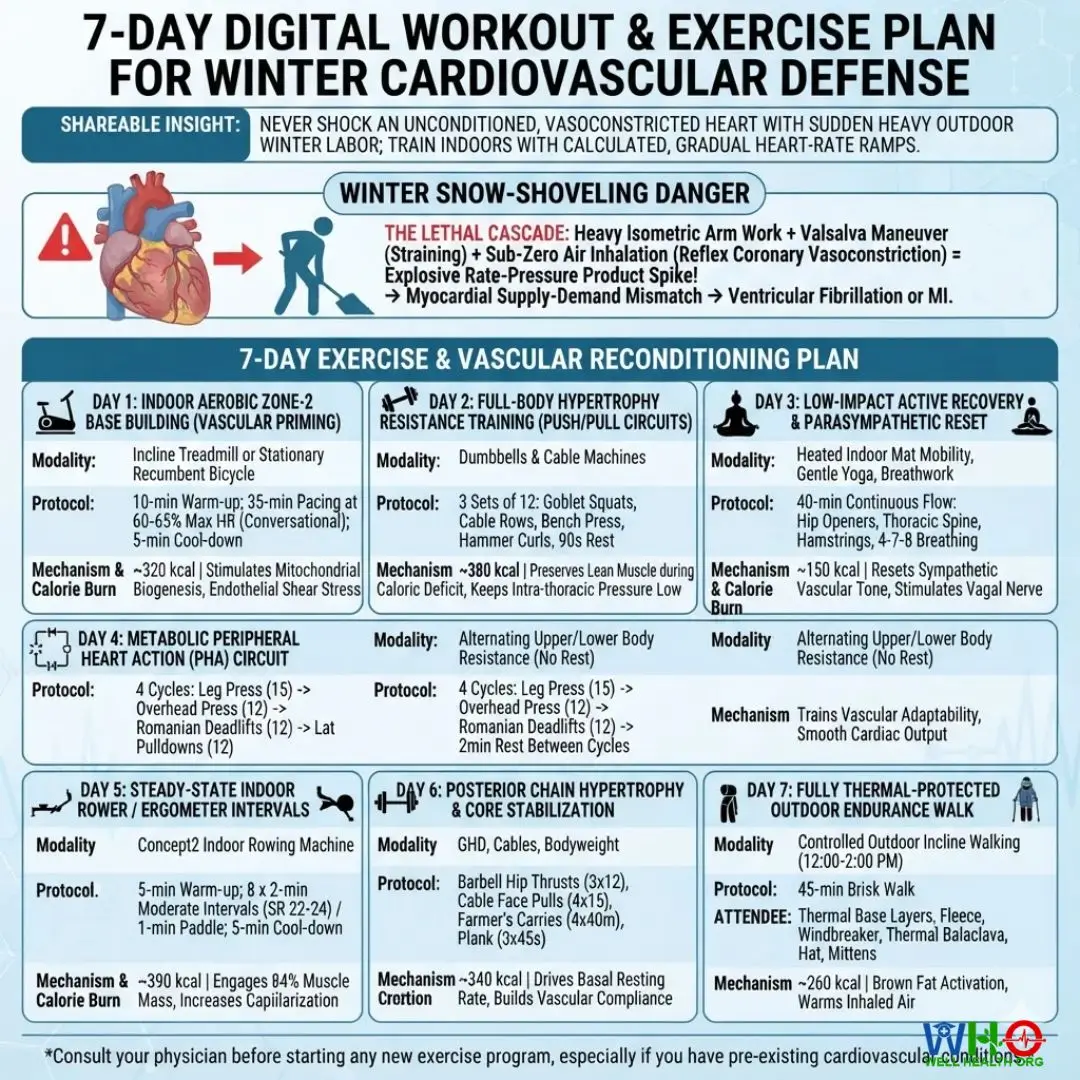
Physical activity in the winter is where most patients make life-threatening errors. The classic scenario is the sedentary individual who wakes up, sees a foot of heavy snow, grabs an aluminum shovel, and marches outdoors into freezing temperatures.
Shoveling snow combines heavy isometric arm work (which causes a sharp reflex rise in blood pressure) with the Valsalva maneuver (holding one’s breath during physical straining, which sends thoracic pressure soaring), all performed while inhaling sub-zero air that triggers immediate reflex coronary vasoconstriction via facial and pulmonary cold receptors. The rate-pressure product (Heart Rate × Systolic Blood Pressure)—which directly reflects myocardial oxygen consumption—explodes into the danger zone. If your coronary arteries are stenosed, this sudden surge creates an immediate myocardial supply-demand mismatch, leading straight to acute ventricular fibrillation or myocardial infarction.
Our 7-day protocol shifts conditioning indoors to temperature-controlled settings between 19°C and 22°C (66°F to 72°F). This protects your cardiovascular system from severe vasoconstriction while applying controlled muscular tension that stimulates adipose lipolysis, increases GLUT-4 glucose transporter translocation, and maintains active lean muscle tissue.
🏃♂️ 7-Day Digital Exercise & Vascular Reconditioning Plan
Modality: Incline Treadmill or Stationary Recumbent Bicycle.
Protocol: 10-minute warm-up at low resistance; 35 minutes continuous pacing at 60–65% of Max Heart Rate (Zone 2 conversational pace); 5-minute cool-down.
Mechanism & Calorie Burn: ~320 kcal. Stimulates mitochondrial biogenesis in skeletal muscle without triggering sympathetic norepinephrine spikes; stimulates basal capillary dilation and endothelial shear stress.
Modality: Dumbbells and Cable Machines (Avoid extreme heavy singles).
Protocol: Dumbbell Goblet Squats (3 sets of 12 reps), Seated Cable Rows (3 sets of 12 reps), Dumbbell Flat Bench Press (3 sets of 10 reps), Standing Dumbbell Hammer Curls (3 sets of 12 reps). Rest 90 seconds between sets with steady nasal breathing.
Mechanism & Calorie Burn: ~380 kcal. Heavy reliance on slow-twitch and fast-twitch type IIa motor units. Prevents muscle loss during caloric deficit while keeping intra-thoracic pressure low.
Modality: Heated Indoor Mat Dynamic Mobility, Gentle Yoga, and Deep Diaphragmatic Breathwork.
Protocol: 40 minutes of continuous flow focusing on hip openers, thoracic spine extension, hamstring length, and 4-7-8 breathing patterns.
Mechanism & Calorie Burn: ~150 kcal. Resets hyperactive sympathetic vascular tone; stimulates vagal nerve activity; drops resting peripheral vascular resistance.
Modality: Alternating Upper and Lower Body Resistance without rest.
Protocol: 4 continuous cycles: Leg Press (15 reps), immediately to Dumbbell Overhead Press (12 reps), immediately to Romanian Deadlifts (12 reps), immediately to Lat Pulldowns (12 reps). Rest 2 minutes between cycles.
Mechanism & Calorie Burn: ~450 kcal. PHA circuits force blood to continuously circulate between upper and lower body segments, training vascular adaptability and challenging the microcirculation while keeping cardiac output smooth and steady.
Modality: Concept2 Indoor Rowing Machine.
Protocol: 5-minute warm-up; 8 intervals of 2 minutes at moderate pace (stroke rate 22-24) alternated with 1 minute of light active paddle; 5-minute cool-down.
Mechanism & Calorie Burn: ~390 kcal. Engages 84% of total muscle mass simultaneously. Increases total muscular capillarization without cold airway irritation.
Modality: Glute Ham Developers, Cables, and Bodyweight.
Protocol: Barbell Hip Thrusts (3 sets of 12 reps), Cable Face Pulls (4 sets of 15 reps), Standing Farmer’s Carries (4 walks of 40 meters with moderate dumbbells), Plank holds (3 sets of 45 seconds).
Mechanism & Calorie Burn: ~340 kcal. Strengthens large posterior muscle groups that consume glucose and drive basal resting metabolic rate; builds vascular compliance.
Modality: Controlled Outdoor Incline Walking (Strictly between 12:00 PM and 2:00 PM at peak daylight warmth).
Protocol: 45 minutes of brisk walking. Attire must include thermal base layers, moisture-wicking fleece, windbreaker, thermal balaclava covering mouth and nose, warm hat, and windproof mittens.
Mechanism & Calorie Burn: ~260 kcal. Controlled winter exposure encourages brown fat metabolic activation; warming inhaled air with a balaclava prevents reflex coronary spasms.
How to Keep Muscles Stable & Build Lean Mass While Losing Weight
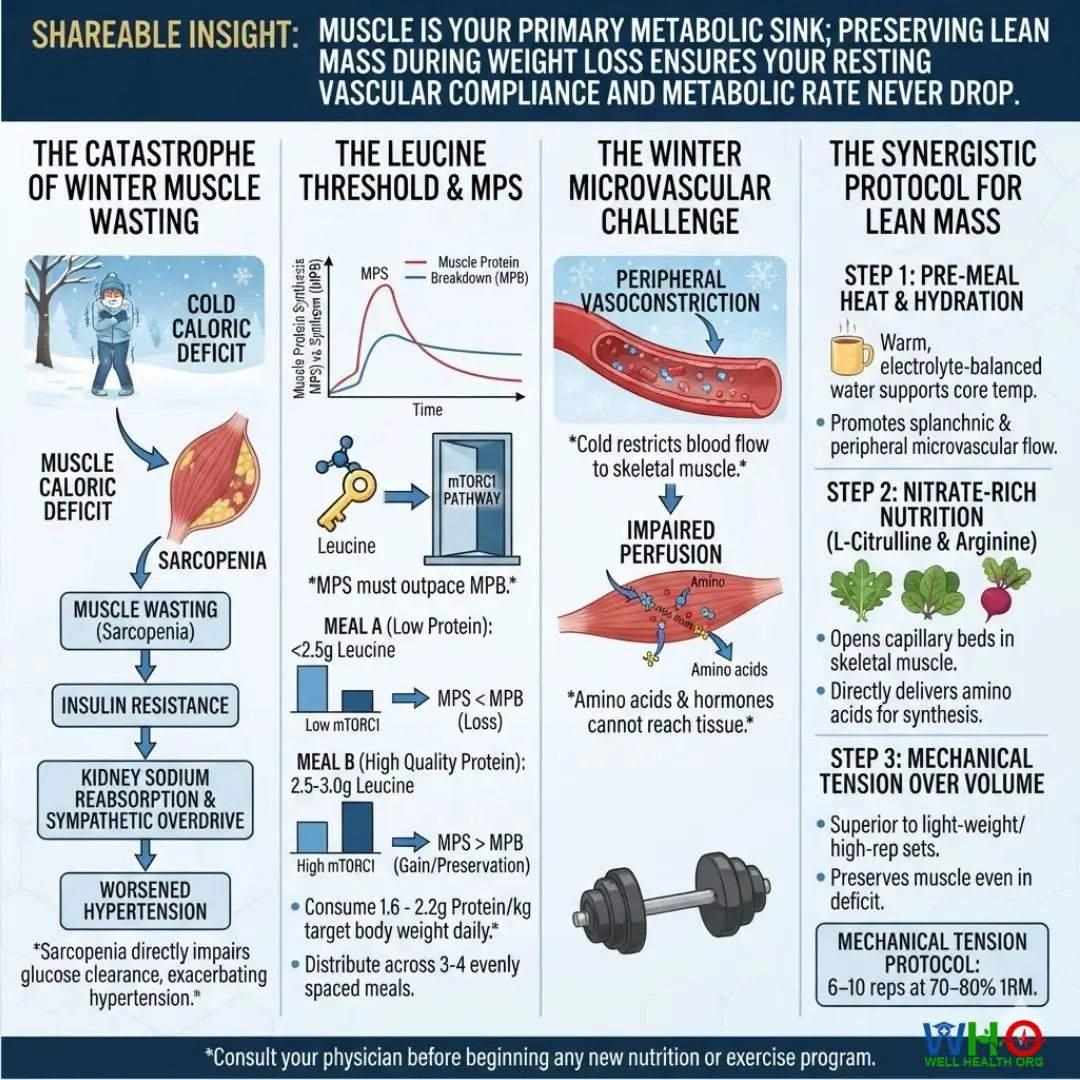
One of the most catastrophic mistakes individuals make during winter fat-loss attempts is sacrificing skeletal muscle tissue. When you enter a caloric deficit without a deliberate strategy to preserve lean mass, your body adapts conservatively: it breaks down metabolically demanding skeletal muscle to reduce energy requirements while desperately clinging to stubborn visceral and subcutaneous fat depots.
Halting Catabolic Muscle Wasting in Caloric Deficits
From a clinical perspective, muscle wasting (sarcopenia) directly worsens hypertension. Skeletal muscle is the primary organ responsible for insulin-mediated glucose clearance, accounting for up to 80% of total glucose disposal. When you lose muscle mass, insulin resistance worsens. Elevated insulin levels directly signal the kidneys to reabsorb sodium, while simultaneously over-activating the sympathetic nervous system and narrowing blood vessels.
To prevent the catabolism of lean tissue during weight loss, we must manage the balance between Muscle Protein Synthesis (MPS) and Muscle Protein Breakdown (MPB). During winter caloric deficits, MPB runs high due to elevated baseline cortisol levels. To override this, you must hit an optimal Leucine Threshold at every feeding window.
Leucine is the essential branched-chain amino acid that acts as the molecular key to turn on the mTORC1 (mechanistic target of rapamycin complex 1) pathway. Without reaching roughly 2.5 to 3.0 grams of leucine in a meal, mTORC1 activation remains low, and MPS will not outpace MPB. This requires consuming 1.6 to 2.2 grams of high-quality protein per kilogram of target body weight daily, distributed evenly across three or four meals rather than lumped into a single evening dinner.
Microvascular Perfusion, Leucine Thresholds, and Muscle Synthesis
However, getting protein into your digestive tract is only half the battle. In cold weather, peripheral vasoconstriction restricts blood flow to your skeletal musculature. If microvascular perfusion is impaired, amino acids and hormones cannot reach muscle tissue efficiently.
This is where our combined nutritional and training protocol works together synergistically:
- Pre-Meal Heat & Hydration: Drinking warm, electrolyte-balanced water before high-protein meals supports core temperature and promotes splanchnic and peripheral microvascular blood flow.
- Targeted L-Citrulline & Arginine Rich Nutrition: Consuming nitrate-rich foods (arugula, spinach, beets) supports nitric oxide production, which opens capillary beds in skeletal muscle tissue. This delivers essential amino acids directly to muscle beds for protein synthesis.
- Mechanical Tension Over Volume: To signal your DNA to preserve muscle mass, heavy-load, low-rep mechanical tension (e.g., 6–10 reps at 70–80% 1RM) is clinically superior to light-weight, high-rep endurance sets. High mechanical tension signals that muscle tissue is essential for survival, suppressing catabolic pathways like myostatin even while in a caloric deficit.
Doctor’s Bottom Line & Motivational Ending
After three decades of walking the halls of intensive care units, neurology wards, and cardiology clinics, I can tell you this with clinical certainty: biology is unapologetically honest. It does not care about our excuses, our stressful schedules, or how comfortable it feels to stay warm under a blanket eating salty, calorie-dense foods while our arteries steadily stiffen.
Winter is a relentless stress test for your cardiovascular system. It strips away illusions. If your blood vessels are rigid, inflamed, and handling high pressures, the drop in mercury will expose those weaknesses. But that does not mean you have to be its victim.
Every time you choose a high-potassium, nitrate-dense whole food over an ultra-processed, sodium-laden meal, you are prescribing yourself an organic vasodilator. Every time you complete a focused indoor workout, you are manually pumping anti-inflammatory cytokines through your system and easing the strain on your heart’s left ventricle. Every pound of visceral fat you melt away relieves direct hydraulic resistance from your arterial tree.
Do not wait for a crushing chest pain or a high blood pressure reading in a cold emergency room to shock you into taking action. Reclaim control of your cardiovascular health right now. Layer up, protect your extremities, nourish your vascular endothelium, lift with intention, and watch your body transform into an enduring, high-performance engine that thrives in any season.
Regional Protocols: Navigating Western & Eastern Winter Climates
🌍 Western Climates (United States, United Kingdom, Northern Europe)
The Micro-Climate Challenge: Western populations face central heating dry air (frequently below 20% relative humidity) combined with extreme outdoor drops. Overheated indoor air causes insensible water loss through respiration and perspiration, leading to nocturnal hemoconcentration (thickened blood) that spikes early morning blood pressure.
- Indoor Heating Regulation: Keep your thermostat strictly between 18°C and 21°C (64°F to 70°F). Avoid setting room temperatures above 23°C (73°F), as stepping directly from hot indoor spaces into sub-zero outdoor air triggers an exaggerated vasoconstrictive reflex.
- Ultrasonic Humidification: Maintain indoor humidity at 40% to 50% using cool-mist humidifiers to protect your airway endothelium and prevent silent fluid loss while you sleep.
- Outdoor Protection: When walking outdoors in blizzards or freezing wind, wear a silk or merino wool balaclava over your nose and mouth. This creates a pocket of warmed, humidified air, keeping cold air from irritating respiratory and facial nerve pathways that trigger coronary spasms.
🌏 Eastern & Subtropical Climates (East Asia, South Asia, Middle East Winters)
The Micro-Climate Challenge: In parts of South Asia, East Asia, and Southern Europe, residential housing often lacks central heating or proper insulation. As a result, indoor temperatures can closely mirror damp, chilly outdoor conditions. At the same time, regional winter menus lean heavily on high-sodium comfort broths, salted preserved foods, and soy-based condiments.
- Indoor Cold Exposure: Sleeping in unheated rooms where temperatures fall below 15°C (59°F) keeps blood pressure elevated throughout the night, completely wiping out the normal, healthy nocturnal dip in blood pressure. Use heated blankets to keep your sleeping environment warm.
- Managing Dietary Sodium: Traditional winter hot pots, ramens, instant soups, and preserved meats can deliver up to 5,000 mg of sodium in a single meal. Swap out salt-heavy bases for homemade, unsalted bone broths seasoned with potassium-rich seaweed, fresh ginger, raw garlic, and shiitake mushrooms.
- Air Quality and Inversions: Winter weather patterns often trap fine particulate matter (PM2.5) near the ground. Inhaling these tiny pollutants causes systemic inflammation, raises sympathetic nervous tone, and accelerates arterial vasoconstriction. Check Air Quality Index (AQI) levels daily, run HEPA air purifiers indoors, and avoid exercising outdoors on poor air quality days.
Global Clinical FAQs: Winter Blood Pressure, Weight Loss, and Cardiovascular Safety
Why are my blood pressure readings higher in winter compared to summer?
This seasonal shift is driven by basic human biology. When your skin detects lower temperatures, your sympathetic nervous system narrows your peripheral blood vessels (vasoconstriction) to redirect warm blood toward your vital internal organs and reduce heat loss. This narrowing increases total systemic vascular resistance. In warm summer months, your blood vessels relax and dilate to shed excess heat through the skin, while light sweating gently reduces total fluid volume, both of which naturally lower your blood pressure readings.
Is it safe to exercise outdoors in freezing temperatures if I have high blood pressure?
Only under carefully controlled, low-intensity conditions with full thermal protection. You should avoid sudden, high-intensity workouts—such as heavy snow shoveling, sprinting, or carrying heavy loads outdoors—in temperatures below 4°C (40°F). Breathing in cold air causes coronary arteries to narrow, while high-effort physical strain rapidly elevates both heart rate and blood pressure, creating a dangerous shortage of oxygen to the heart muscle. If you do walk outside, bundle up in warm layers, cover your mouth and nose with a scarf or balaclava to warm the air you breathe, and save your demanding workouts for the gym or living room.
Does taking hot baths or sitting in saunas help lower winter blood pressure?
Saunas and warm baths do relax blood vessels and lower blood pressure while you are in them. However, you must be careful: transitioning rapidly from hot water or steam rooms back into a cold environment can trigger an immediate reflex spike in blood pressure. Additionally, spending too long in hot water can cause widespread peripheral vasodilation; if you stand up too quickly, you may experience a sharp drop in blood pressure (orthostatic hypotension), leading to dizziness or fainting. Keep bath temperatures warm rather than scalding, limit sauna sessions to 15 minutes, cool down gradually, and rehydrate right away.
Why do I feel less thirsty in winter, and how does dehydration affect blood pressure?
Cold temperatures naturally blunt your body’s thirst mechanism by up to 40%. Because cold-induced vasoconstriction shifts more blood volume to your core, your central volume receptors tell the brain that your body is adequately hydrated, even when total water levels are running low. Meanwhile, your kidneys process this shifted fluid volume and increase urine production—a process known as cold diuresis. As you lose fluid, your blood becomes more concentrated and viscous, forcing your heart to work harder to circulate it. Drink warm water, herbal teas, or broths consistently throughout the day, even if you do not feel thirsty.
Can taking an annual flu shot really protect me against heart attacks in winter?
Yes, the protective link is well established in clinical cardiology. Influenza is not simply a respiratory infection; it triggers widespread systemic inflammation, speeds up clotting pathways, and causes significant cardiovascular stress. This acute inflammation can destabilize atheromatous plaques in your coronary arteries, causing them to rupture and form life-threatening clots. Large clinical studies have shown that getting an annual influenza vaccine reduces the risk of major cardiovascular events by 15% to 30% in individuals with high blood pressure and established heart disease.
Should my physician increase my blood pressure medications during the winter?
Many hypertensive patients do require seasonal medication adjustments. If you track your blood pressure carefully at home and notice your readings consistently climb by 10 to 15 mmHg as colder weather sets in, bring your log to your physician. Your doctor may choose to temporarily adjust your dosage or add an evening medication to counter cold-induced morning surges. Never alter, double, or stop your blood pressure prescriptions on your own without direct clinical supervision.
Medically Reviewed by Prof. Dr. Akram
Orthopedic Surgeon | Professor | Senior Medical Specialist
Prof. Dr. Akram is a distinguished surgeon with over 15 years of clinical expertise. Having served as a lead Emergency Specialist at Complex International Government Hospital, he currently leads a specialized team of 13 medical professionals at his private hospital. As a Professor at top medical universities, he ensures that every article on WellHealthOrg.com meets rigorous clinical standards.
Medical Disclaimer:
The information provided is for educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult your physician for any medical concerns.
Our content is rigorously fact-checked by our 13-member Editorial Team under the clinical supervision of Prof. Dr. Akram.







