

🩺 Dr. Akram’s Private Clinical Notes for Heartburn and Acidity in Pregnancy
“Across three decades in tertiary neurology and systemic clinical medicine, I have treated hundreds of pregnant patients who arrive at my clinic convinced they are experiencing cardiovascular emergencies or complex vagal neuropathies. One vivid case was Elena, a 31-year-old architectural engineer from Chicago, carrying twins at 26 weeks gestation. She sat trembling in my examination room, hollow-eyed from four days of complete sleep deprivation. She described a corrosive, white-hot retrosternal fire that clawed up into her throat every time she reclined, triggering paroxysms of dry-heaving and sinus tachycardia. Her obstetric team had brushed it off with a casual: ‘It’s just third-trimester baby hair, take a peppermint.’ That dismissive folklore was not merely unscientific; it was dangerous. Her esophageal mucosa was raw, her hydration was compromised, and her autonomic system was firing on all cylinders due to untreated pain and severe nausea. Pregnancy-related gastroesophageal reflux disease is not a benign rite of passage; it is an aggressive physiological cascade involving smooth muscle relaxation, mechanical displacement, and enteric dysmotility. When we initiated a calibrated clinical protocol—separating her prenatal micronutrients, introducing targeted antacid barriers, and escalating safely to an H2 blocker—Elena slept eight unbroken hours within forty-eight hours. Her maternal-fetal metrics stabilized immediately. No expectant mother should have to endure chemical burns in her esophagus under the guise that suffering is an inevitable tax of motherhood.”
Table of Contents: Evidence-Based Clinical Guide
- 1. What is Heartburn and Acid Reflux in Pregnancy?
- 2. The Root Causes: Hormonal, Mechanical, and Lifestyle Drivers
- 2.1 Progesterone’s Direct Smooth Muscle Relaxation on the LES
- 2.2 Estrogen, Motilin, and Prolonged Gastric Transit
- 2.3 The Gravid Uterus: Elevating Intra-Abdominal Pressure
- 2.4 Dietary Triggers: Western Ultra-Processed Foods vs. Asian Spices
- 2.5 The Aggravating Feedback Loop: Reflux and NVP (PUQE Metrics)
- 3. Advanced Medical Treatments: A Stepwise Pharmacotherapy Ladder
- 4. Proven Home Remedies and Non-Pharmacological Interventions
- 5. Doctor’s Final Verdict & Clinical Management Roadmap
- 6. Geographic and Cultural Adaptation Strategies
- 7. Global Frequently Asked Questions (Maternal GERD)
1. What is Heartburn and Acid Reflux in Pregnancy?
1.1 Defining Maternal Pyrosis and GERD
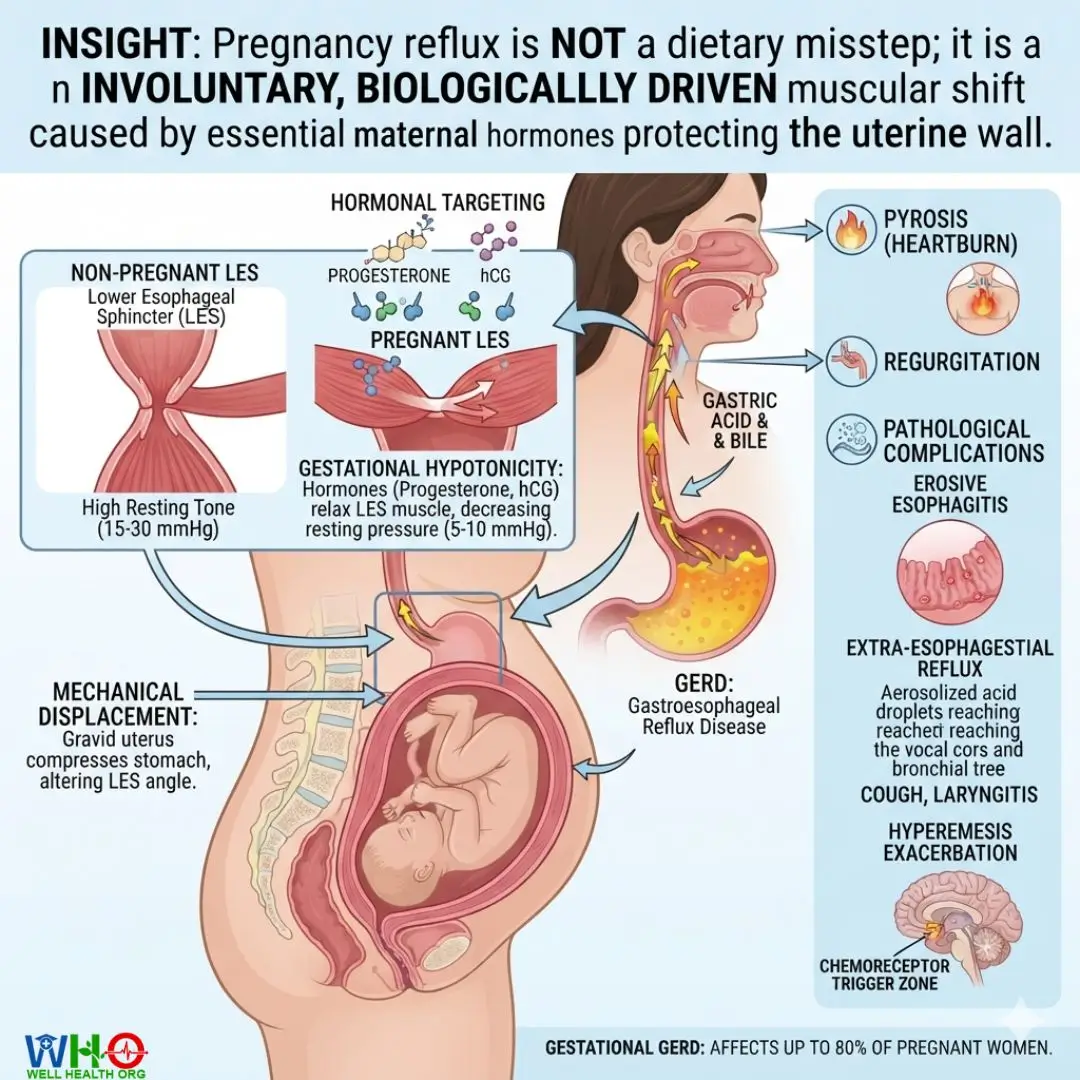
Heartburn, clinically termed pyrosis, is characterized by a burning sensation located directly behind the sternum, radiating upward toward the manubrium, the suprasternal notch, and frequently reaching the pharynx. When this retrosternal discomfort is accompanied by the passive regurgitation of corrosive gastric juice into the upper aerodigestive tract, it enters the diagnostic spectrum of Gastroesophageal Reflux Disease (GERD). In the non-pregnant population, GERD is frequently driven by chronic obesity, hiatus hernia, or lifestyle-induced lower esophageal incompetence. In contrast, gestational GERD is a unique, self-limiting yet profoundly debilitating clinical entity that strikes up to 80% of pregnant women globally, cutting across all geographic, genetic, and socio-economic demographics.
The symptom onset typically follows a predictable biphasic curve. Some women encounter early symptoms in the first trimester, directly matching initial shifts in human chorionic gonadotropin (hCG) and circulating progesterone. However, the prevalence reaches its peak in the late second and third trimesters, where structural and mechanical factors combine with these chemical triggers. For decades, traditional medicine dismissed pregnancy heartburn as a benign nuisance, an inescapable footnote in an otherwise healthy pregnancy. However, rigorous clinical evidence demonstrates that unmanaged pyrosis triggers progressive mucosal erosions, disrupts vital maternal restorative sleep patterns, and magnifies the nausea and vomiting of pregnancy (NVP), with severe consequences for maternal mental health and nutritional equilibrium.
1.2 The Triad: Hormones, Motility, and Mechanics
To effectively manage this condition, we must understand its physiology. Gastroesophageal reflux in an expecting mother is governed by a precise biological triad:
- Hormonal Hypotonicity: Circulating gestational hormones directly target the smooth muscle fibers of the Lower Esophageal Sphincter (LES), decreasing resting closing pressure.
- Gastric Hypomotility: Slower smooth muscle contractions delay the clearance of food and acidic secretions from the stomach, keeping the gastric pool full for longer periods.
- Mechanical Displacement: As the fetus grows, the physical expansion of the gravid uterus alters abdominal anatomy, compressing the stomach upward and changing its resting angle.
In a non-pregnant individual, the Lower Esophageal Sphincter acts as a high-pressure zone, maintaining a resting tonus between 15 to 30 millimeters of mercury (mmHg) higher than intragastric pressure. This muscular barrier prevents stomach contents from backwashing into the delicate, non-keratinized squamous epithelium of the esophagus. During pregnancy, this protective barrier falters. Chemical messengers designed to keep the myometrium (uterine muscle) relaxed and receptive to fetal growth also act on the digestive tract, relaxing the lower esophageal valve. When that barrier pressure falls below 5 to 10 mmHg, even basic movements—such as bending over to tie a shoe, shifting in bed, or sitting back after a light meal—allow stomach acid, pepsin, and bile to escape directly into the unprotected esophagus.
1.3 Physiological Reflux vs. Pathological Complications
Obstetric clinicians and general practitioners must know when ordinary gestational reflux crosses over into pathological territory. While standard physiological pyrosis is predictably postprandial (worse after eating) or postural (worse when lying flat) and resolves with basic clinical interventions, unchecked pathological GERD can lead to serious health complications:
- Erosive Esophagitis: Direct chemical de-epithelialization of the esophageal lining, leading to micro-ulcerations, microvascular oozing, and unexplained maternal iron-deficiency anemia.
- Odynophagia and Dysphagia: Painful or difficult swallowing caused by localized tissue edema, esophageal spasm, or inflammation near the gastroesophageal junction.
- Extra-Esophageal Reflux (Atypical GERD): Micro-aspiration of aerosolized acid droplets into the vocal cords and bronchial tree, triggering chronic nocturnal cough, laryngitis, wheezing, and aggravating pre-existing maternal bronchial asthma.
- Hyperemesis Exacerbation: Acid reflux keeps the chemoreceptor trigger zone in the brainstem hyper-sensitized, turning manageable morning sickness into severe, dehydrating pregnancy vomiting.
2. The Root Causes: Hormonal, Mechanical, and Lifestyle Drivers
2.1 Progesterone’s Direct Smooth Muscle Relaxation on the LES
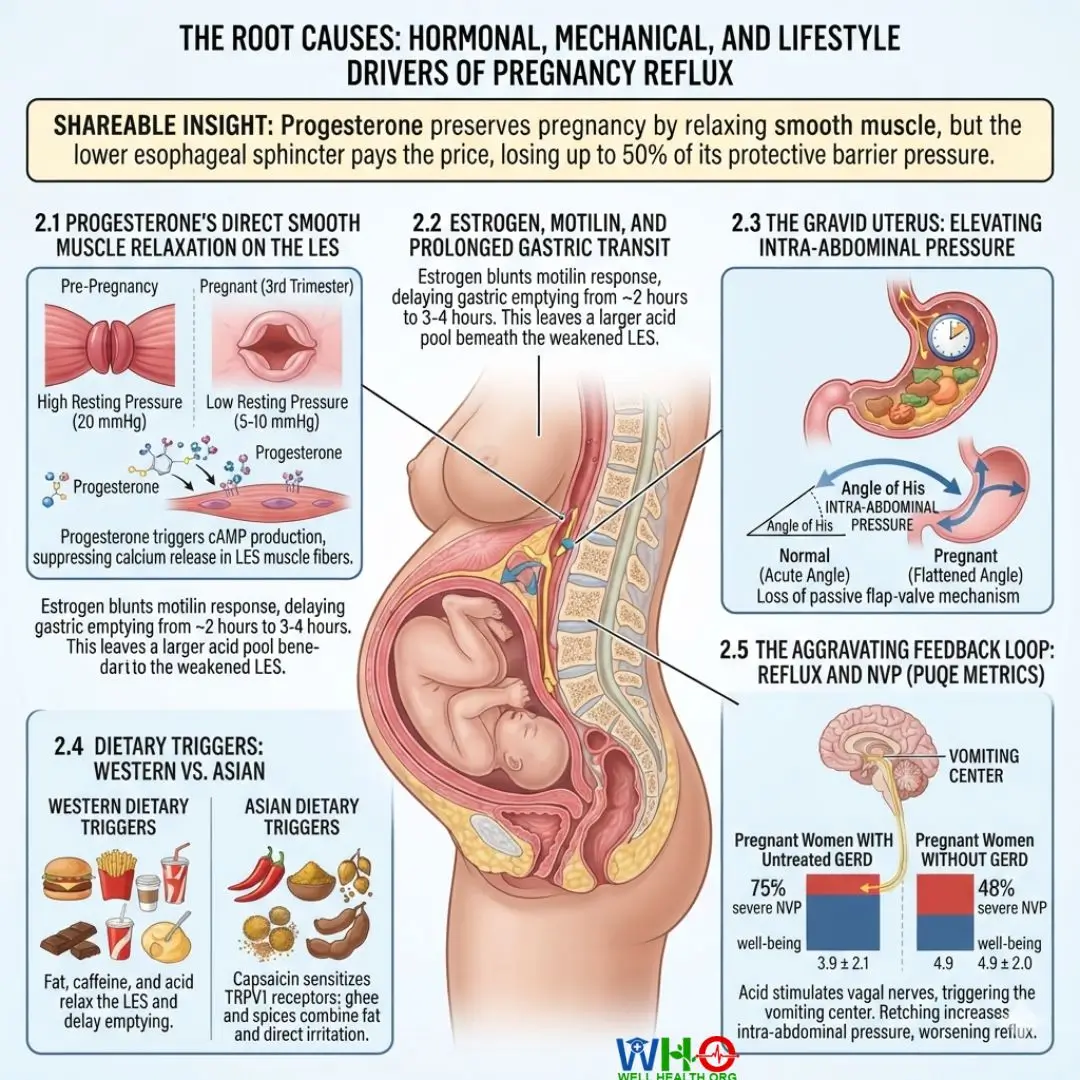
Progesterone is the primary chemical driver behind pregnancy heartburn. Synthesized initially by the corpus luteum and later taken over in massive quantities by the syncytiotrophoblast of the developing placenta, progesterone binds directly to specific nuclear receptors located within gastrointestinal smooth muscle cells. This binding stimulates cyclic adenosine monophosphate (cAMP) production and suppresses intracellular calcium release within the circular muscle fibers of the lower esophageal sphincter.
The natural evolutionary purpose of this mechanism is clear: it calms the myometrium, preventing preterm uterine contractions and allowing the fetus to grow safely. However, the digestive tract shares these identical smooth muscle receptors. As a result, the systemic surge in progesterone causes a generalized relaxation of gastrointestinal valves. High-resolution esophageal manometry studies demonstrate that the resting pressure of the lower esophageal sphincter drops progressively through each trimester, falling from a robust pre-pregnancy baseline of approximately 20 mmHg down to single digits in late pregnancy. This sharp reduction turns a once airtight muscular seal into a lax, permeable boundary.
2.2 Estrogen, Motilin, and Prolonged Gastric Transit
While progesterone relaxes the physical valves, estrogen acts on the stomach’s electrical pacing and rhythmic contractions. Elevated 17-beta-estradiol, combined with progesterone, blunts normal responses to motilin—the primary peptide hormone responsible for stimulating rhythmic migrating motor complexes in the stomach and small intestine.
This causes a dramatic slowdown in gastric motility. Solid meals that would typically pass from the stomach into the duodenum within 90 to 120 minutes can linger in the maternal stomach for three to four hours. This delayed gastric emptying leaves a pool of hydrochloric acid and digestive enzymes sitting directly beneath a relaxed esophageal valve. The longer food stays in the stomach, the more gastrin is secreted, increasing both the volume and acidity of the stomach contents waiting to push upward into the esophagus.
2.3 The Gravid Uterus: Elevating Intra-Abdominal Pressure
As pregnancy progresses past the 20th week, physical anatomy changes rapidly. The growing fetus, expanding placenta, and volume of amniotic fluid combine to push the uterus high into the abdominal cavity. By the 32nd to 36th weeks, the uterine fundus reaches the xiphoid process, compressing the intestinal loops and displacing the stomach superiorly and laterally toward the left hypochondrium.
This physical crowding creates two mechanical problems. First, it significantly increases baseline intra-abdominal pressure, directly opposing the already weakened closure pressure of the lower esophageal sphincter. Second, this upward compression distorts the Angle of His—the natural anatomical junction between the esophagus and the stomach that typically acts as a passive anti-reflux flap-valve. Once flattened by the rising uterus, this natural flap mechanism fails entirely, allowing gastric acid to slip upward whenever the patient reclines, bends forward, or wears restrictive clothing.
2.4 Dietary Triggers: Western Ultra-Processed Foods vs. Asian Spices
While underlying hormones and anatomy set the stage, dietary habits trigger immediate symptoms. Reflux triggers vary considerably across different culinary cultures, highlighting how varied diets affect the gastroesophageal junction:
- Western Dietary Triggers (US, UK, Northern Europe): Heavy consumption of ultra-processed foods rich in saturated lipids (deep-fried proteins, buttery pastries, and processed meats). High fat intake triggers cholecystokinin (CCK) release from the duodenum, which further relaxes the esophageal sphincter and delays stomach emptying. Combined with acidic tomatoes, citrus juices, carbonated beverages, chocolate (which contains methylxanthines that relax the sphincter), and caffeine, this diet keeps the stomach full and acidic.
- Asian Dietary Triggers (South, East, and Southeast Asia): Traditional culinary foundations feature concentrated capsaisin (found in bird’s-eye chilies, cayenne, and fresh peppers), ground black mustard seeds, high-acid tamarind pastes, and heavy garlic or raw onion reductions. Capsaicin stimulates transient receptor potential vanilloid-1 (TRPV1) receptors across the esophageal lining, dramatically increasing pain sensitivity and inducing localized inflammation. In South Asian communities, foods prepared with trans-fat-heavy clarified butter (ghee), paired with strong spices, combine the delayed gastric emptying of high-fat foods with the direct burning irritation of pungent spices.
2.5 The Aggravating Feedback Loop: Reflux and NVP (PUQE Metrics)
A common clinical mistake is viewing morning sickness (Nausea and Vomiting of Pregnancy, or NVP) and acid reflux as separate problems. They are tightly linked. Landmark research conducted by the Canadian Motherisk Program clearly revealed that untreated GERD directly worsens the severity and duration of NVP.
In a well-known prospective cohort trial evaluating 382 pregnant women, researchers used the validated Pregnancy-Unique Quantification of Emesis and Nausea (PUQE) scoring system, which quantifies nausea duration, vomiting episodes, and retching paroxysms over 24 hours. The clinical data showed a striking connection:
- Among pregnant women suffering from NVP without concurrent acid reflux, 48% fell into the severe NVP clinical categorization.
- Among women battling both NVP and active, untreated GERD, 75% were classified as having severe NVP (PUQE > 13).
- Maternal well-being scores (ranging from 0 = worst to 10 = optimal) averaged 4.9 ± 2.0 in the control group, but plummeted to 3.9 ± 2.1 (P = .0004) in mothers with untreated heartburn.
When acid washes back into the proximal esophagus and posterior oropharynx, it triggers sensitive glossopharyngeal and vagal nerve afferents. This triggers the vomiting center in the brainstem, causing retching. Retching, in turn, spikes intra-abdominal pressure and forces more concentrated gastric acid up into the chest, creating a worsening cycle of pain and nausea. When acid-reducing therapies were introduced to these patients in a follow-up trial of 60 women, their PUQE scores dropped significantly from 9.6 ± 3.0 down to 6.5 ± 2.5 (P < .0001), while their well-being ratings jumped from 4.0 ± 2.0 to 6.8 ± 1.6 (P < .0001). Treating acid reflux is not an optional comfort measure—it is a vital medical step to control severe nausea and vomiting in pregnancy.
3. Advanced Medical Treatments: A Stepwise Pharmacotherapy Ladder

Managing acid reflux in pregnancy requires a careful, stepwise approach. If standard dietary adjustments and physical modifications do not provide sufficient relief within 48 to 72 hours, clinicians should step up pharmacotherapy systematically. The goal is simple: achieve full symptom relief and protect the esophageal lining using medications with proven safety profiles for both mother and child.
3.1 Step 1: Safe Mineral Antacids & Alginate Rafts
⚡ Clinical Application: Administer chewable or liquid calcium carbonate or combined aluminum hydroxide/magnesium hydroxide formulations immediately following symptomatic triggers, or 45 to 60 minutes after meals and directly before retiring to bed. Where accessible, prefer alginate-based oral suspensions (e.g., sodium alginate combined with low-dose calcium carbonate). Alginates react with gastric hydrochloric acid to precipitate into a neutral, low-density viscous foaming gel (a mechanical “raft”) that floats on the surface of the chyme, creating an inert physical barrier across the gastroesophageal junction.
⚖️ Dosage (US/Metric): Calcium Carbonate: 500 mg to 1000 mg per oral dose as needed. Absolute ceiling limit: Never exceed 1,500 mg of elemental calcium per 24-hour cycle from all dietary and supplementary sources combined (equivalent to roughly 3.75 g of calcium carbonate salt). Alginate suspensions: 5 to 10 mL post-prandially.
🔬 Mechanism of Action: Calcium carbonate directly neutralizes hydrochloric acid via the chemical reaction: CaCO₃ + 2HCl → CaCl₂ + H₂O + CO₂. This rapidly raises the intragastric pH above 3.5 to 4.0, deactivating proteolytic pepsin. Alginate components precipitate into an alginic acid raft possessing near-neutral pH, which effectively prevents acid, pepsin, and bile from contacting the esophageal mucosa.
⚠️ Medical Warning: Never exceed 1,400 to 1,500 mg daily of elemental calcium to avoid hypercalcemia, metabolic alkalosis, and renal compromise (Milk-Alkali Syndrome). Magnesium-containing formulas may cause dose-dependent osmotic diarrhea; aluminum formulas can worsen pregnancy-induced constipation.
3.2 Step 2: Histamine-2 Receptor Antagonists (H2RAs)
⚡ Clinical Application: Step up to H2-receptor antagonists when antacids fail to control daily pain, night-time waking, or reflux-driven vomiting. Famotidine serves as the modern first choice across obstetric units worldwide due to its clean pharmacology, replacing historical ranitidine formulations. Administer orally once daily at bedtime for nocturnal reflux, or twice daily 30 minutes before morning and evening meals for persistent daytime symptoms.
⚖️ Dosage (US/Metric): Famotidine: 10 mg to 20 mg orally twice daily (or a single 20 mg to 40 mg dose at bedtime). Cimetidine: 400 mg twice daily (historically validated, though less preferred due to weak anti-androgenic potential and minor hepatic CYP450 interactions).
🔬 Mechanism of Action: Competitively and selectively antagonizes H2 receptors located on the basolateral membranes of gastric parietal cells. By blocking histamine signaling, it shuts down intracellular cyclic adenosine monophosphate (cAMP) pathways, reducing basal and stimulated gastric acid secretion by 60% to 70% over a 10- to 12-hour window.
⚠️ Medical Warning: A large meta-analysis evaluating 2,398 women exposed to H2RAs during their first trimester demonstrated an odds ratio of 1.14 (95% CI: 0.89–1.45) for major congenital malformations, confirming no statistically significant teratogenic risk compared to controls. Watch for tachyphylaxis (tolerance), which can develop within 10 to 14 days of continuous daily dosing.
3.3 Step 3: Proton Pump Inhibitors (PPIs) in Refractory Cases
⚡ Clinical Application: Indicated for severe, intractable GERD, endoscopically confirmed erosive esophagitis, severe PUQE scores unresponsive to combined antiemetic/H2RA regimens, or suspected microscopic pulmonary aspiration. PPIs must be taken strictly 30 to 60 minutes before the first meal of the morning with water to ensure peak drug concentrations coincide with active meal-stimulated proton pump activity.
⚖️ Dosage (US/Metric): Omeprazole: 20 mg once daily (expandable to 40 mg daily in severe refractory reflux under specialist care). Alternative verified profiles: Pantoprazole 20 mg to 40 mg daily; Lansoprazole 15 mg to 30 mg daily; Esomeprazole 20 mg to 40 mg daily.
🔬 Mechanism of Action: Passes through parietal cells as an inactive prodrug and accumulates within the acidic canaliculi. There, it transforms into an active sulfonamide that forms irreversible covalent disulfide bonds with cysteine residues on the hydrogen-potassium ATPase pump (H+/K+ ATPase). This action permanently disables the final step of acid secretion, providing up to 24 hours of sustained hypochlorhydria until new enzyme pumps can be synthesized.
⚠️ Medical Warning: A comprehensive meta-analysis of 1,530 pregnant women exposed to PPIs during organogenesis demonstrated an odds ratio of 1.12 (95% CI: 0.84–1.45) for congenital malformations, confirming their fetal safety. However, long-term continuous use can impair intestinal absorption of non-heme iron and vitamin B12, requiring regular monitoring of maternal serum ferritin and hemoglobin levels.
3.4 Pharmacokinetic Clashes: Prenatal Iron and Folic Acid
One common prescribing misstep in prenatal medicine is overlooking the physical and chemical interactions between acid medications and routine pregnancy vitamins. Calcium carbonate, magnesium hydroxide, and aluminum salts can bind to prenatal iron supplements in the gut lumen, forming insoluble, non-absorbable chelates that pass straight through the bowel. This wastes maternal iron stores, worsening gestational anemia and fatigue.
Furthermore, iron salts require an acidic gastric environment (pH < 3.0) to reduce dietary ferric iron (Fe3+) into the absorbable ferrous form (Fe2+). If an antacid is taken concurrently, it neutralizes that acid window and drops iron absorption by up to 70%.
⏰ The Clinical Two-Hour Separation Rule: Never take antacids, H2 blockers, or alginate suspensions within a minimum of 2 hours before or after taking oral prenatal micronutrients, specifically ferrous sulfate, ferrous fumarate, or folic acid formulations. Administer iron supplements during a low-reflux daytime window alongside a modest source of ascorbic acid (such as diluted lemon water) to maintain healthy absorption.
3.5 Absolute Contraindications: Sodium Bicarbonate & Magnesium Trisilicate
⚡ Clinical Application: STRICT AVOIDANCE. Remove all domestic home solutions containing basic baking soda (sodium bicarbonate), sparkling alkaline effervescent powders, and outdated antacid blends containing magnesium trisilicate from the patient’s medicine cabinet.
⚖️ Dosage (US/Metric): Zero clinical dose. Any systemic ingestion of sodium bicarbonate exceeding standard culinary baking trace amounts is contraindicated during all trimesters.
🔬 Mechanism of Action: Sodium bicarbonate rapidly absorbs across the gastroduodenal mucosa into systemic circulation. This introduces an acute, exogenous alkaline load that disrupts the delicate maternal renal-bicarbonate axis, shifting blood pH toward systemic metabolic alkalosis. Concurrently, the excessive sodium load drives vascular volume expansion, triggering interstitial water retention and worsening maternal gestational hypertension.
⚠️ Medical Warning: Chronic use of sodium bicarbonate carries high risks of maternal-fetal metabolic alkalosis, acute fluid retention, and sudden blood pressure spikes in women susceptible to pre-eclampsia. Prolonged use of magnesium trisilicate is directly associated with fetal nephrolithiasis (kidney stones), neonatal muscular hypotonia (floppy infant syndrome), and severe neonatal respiratory depression at delivery. These agents are unsafe in modern obstetrics.
4. Proven Home Remedies and Non-Pharmacological Interventions
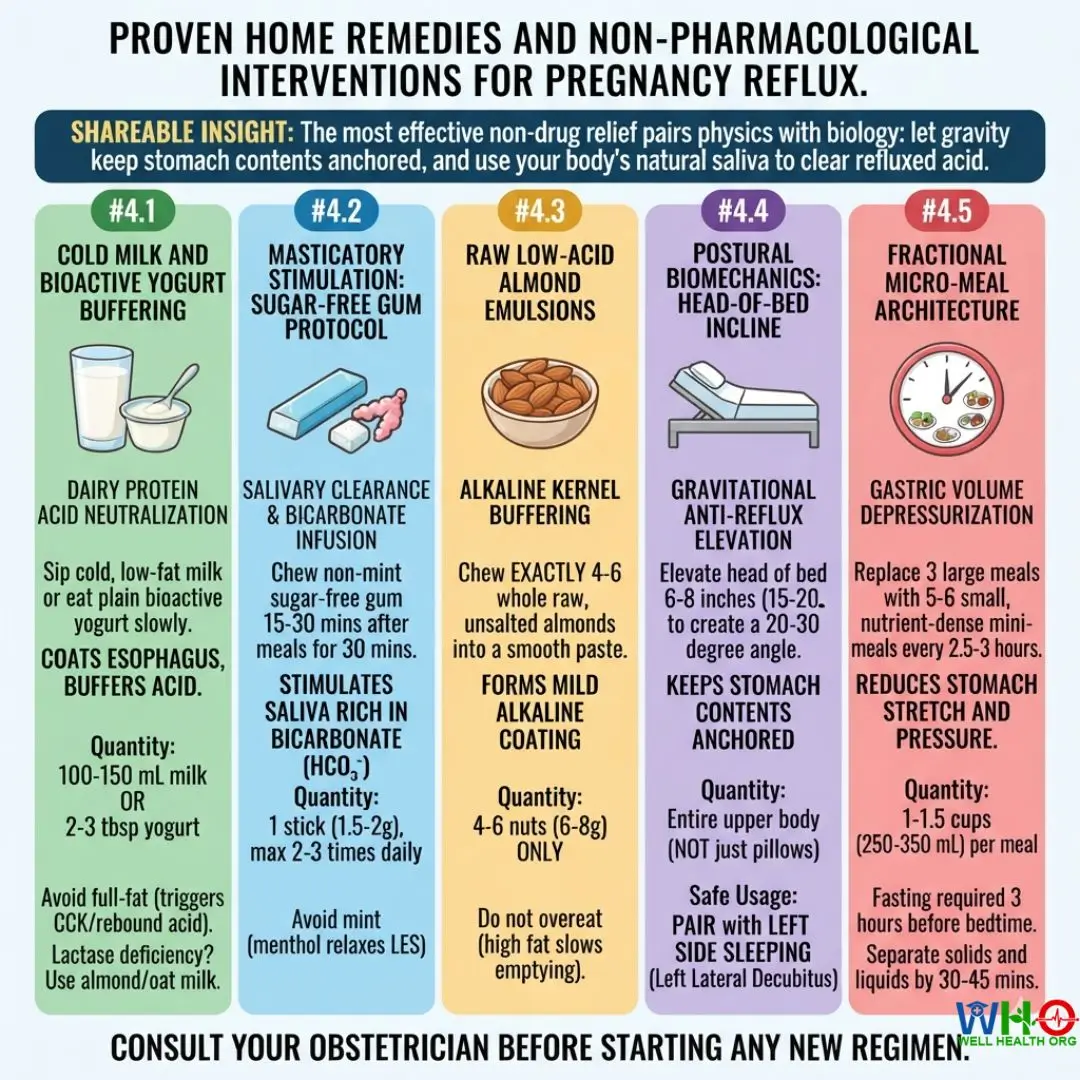
Non-pharmacological interventions are the essential foundation of heartburn management in pregnancy. For mild to moderate symptoms, targeted home strategies can reduce reflux events without medication. When medications are required, these practices work alongside them to lower the necessary drug doses.
4.1 Cold Milk and Bioactive Yogurt Buffering
⚡ Preparation & Use: Pour plain, unsweetened, cold semi-skimmed or low-fat milk into a glass, or measure plain bioactive yogurt (free of added sucrose, corn syrup, or sour fruit purees). Drink or eat slowly in small sips or spoonfuls during an active acute heartburn episode.
⚖️ Quantity (US/Metric): 100 mL to 150 mL (approximately 3.5 to 5 fluid ounces) of cold milk, or 2 to 3 rounded tablespoons (approximately 45–60 grams) of set plain yogurt.
🔬 Natural Healing Process: Liquid milk and smooth yogurt immediately coat the inflamed, acid-exposed sensory nerves of the esophageal lining, providing rapid cooling relief. The intrinsic calcium and natural casein/whey proteins bind free hydrogen ions within the gastric lumen, temporarily buffering stomach pH without stimulating excessive gastrin release.
⚠️ Safe Usage Note: Avoid full-fat whole milk or heavy dairy creams. High fat contents trigger cholecystokinin release in the duodenum, causing the lower esophageal sphincter to relax and stimulating rebound acid secretion 45 to 60 minutes later. Patients with lactase deficiency should use certified pasteurized, unsweetened almond or oat milk alternatives.
4.2 Masticatory Stimulation: Sugar-Free Gum Protocol
⚡ Preparation & Use: Chew one piece of sugar-free gum beginning 15 to 30 minutes after completing lunch or dinner. Continue masticating at a regular, relaxed pace for up to half an hour. Avoid rapid chewing to prevent swallowing excess air (aerophagia).
⚖️ Quantity (US/Metric): 1 standard stick or pellet (approx. 1.5 to 2 grams), sweetened with non-cariogenic xylitol or sorbitol. Limit to 2 to 3 sessions per day.
🔬 Natural Healing Process: The physical act of chewing stimulates cranial nerves V, VII, and IX, increasing resting salivary flow rates from parotid and submandibular glands by over 300%. This saliva is naturally rich in endogenous bicarbonate ions (HCO₃⁻). Swallowing this saliva bathes the esophagus, neutralizing trapped acid droplets and speeding up primary peristaltic waves to clear chyme back into the stomach.
⚠️ Safe Usage Note: Select non-mint varieties (such as plain fruit or mastic flavors). Strong spearmint and peppermint contain menthol, a volatile oil that directly relaxes lower esophageal smooth muscle and can trigger paradoxical reflux. Limit intake if sugar alcohols trigger abdominal gas or loose stools.
4.3 Raw Low-Acid Almond Emulsions
⚡ Preparation & Use: Select raw, unsalted, unroasted whole almonds. Chew each nut slowly and thoroughly into a smooth paste before swallowing. This mastication mixes the nut particles with saliva, forming a mild, alkaline emulsion that lines the distal esophagus.
⚖️ Quantity (US/Metric): Exactly 4 to 6 whole raw almonds (approximately 6 to 8 grams total weight). Do not consume large handfuls.
🔬 Natural Healing Process: Raw almonds have an alkaline ash profile, containing balanced amounts of dietary calcium, potassium, and magnesium bound with healthy monounsaturated fatty acids. When chewed into a fine emulsion, they create a light physical coating over the sensitive mucosa, soothing retrosternal burning and providing gentle acid-binding capacity.
⚠️ Safe Usage Note: Keep portions strictly within the 4-to-6 nut limit. Eating larger amounts introduces concentrated dietary lipids, which slows gastric emptying, stimulates the duodenal break, and worsens acid reflux downstream.
4.4 Postural Biomechanics: Head-of-Bed Incline
⚡ Preparation & Use: Elevate the physical head of your bed frame using solid wooden risers placed directly beneath the headboard posts, or sleep on a dedicated medical-grade dense foam sleeping wedge. The angle must support the entire torso from the waist up. Do not simply pile standard soft pillows under your neck, which bends the cervical spine and increases intra-abdominal pressure.
⚖️ Quantity (US/Metric): Create an incline of 6 to 8 inches (15 to 20 cm), achieving an angle between 20 and 30 degrees from horizontal across the upper body.
🔬 Natural Healing Process: This positional incline uses basic gravity to keep fluid gastric contents anchored at the bottom of the stomach (antrum), preventing them from rising to the gastroesophageal junction. Clinical trials show this elevation reduces nighttime esophageal acid exposure time by over 60%, helps clear nocturnal reflux events much faster, and prevents acid from pooling in the throat.
⚠️ Safe Usage Note: Pair this head-of-bed elevation with sleeping on the left side (the left lateral decubitus position). Sleeping on your left keeps the anatomical gastroesophageal junction positioned above the level of gastric juice, preventing the stomach contents from sloshing back into the esophagus.
4.5 Fractional Micro-Meal Architecture
⚡ Preparation & Use: Divide your daily food intake into 5 to 6 small, nutrient-dense mini-meals spaced roughly 2.5 to 3 hours apart, completely replacing the traditional pattern of three large meals. Stop eating all solid foods at least 3 hours before going to sleep at night.
⚖️ Quantity (US/Metric): Portion each micro-meal to roughly 1 to 1.5 standard cups of volume (250 to 350 mL total displacement per sitting).
🔬 Natural Healing Process: Large meals physically stretch the walls of the stomach, triggering transient lower esophageal sphincter relaxations (TLESRs)—spontaneous reflex openings of the valve that allow acid to rush upward. Small meals prevent this wall stretching, reduce intragastric pressure, and empty into the duodenum much faster.
⚠️ Safe Usage Note: Separate your solid meals from liquid drinks. Drinking large glasses of water or juice during a meal dramatically inflates total stomach volume. Instead, drink fluids between meals, aiming for 30 to 45 minutes before or after eating solid foods.
5. Doctor’s Final Verdict & Clinical Management Roadmap
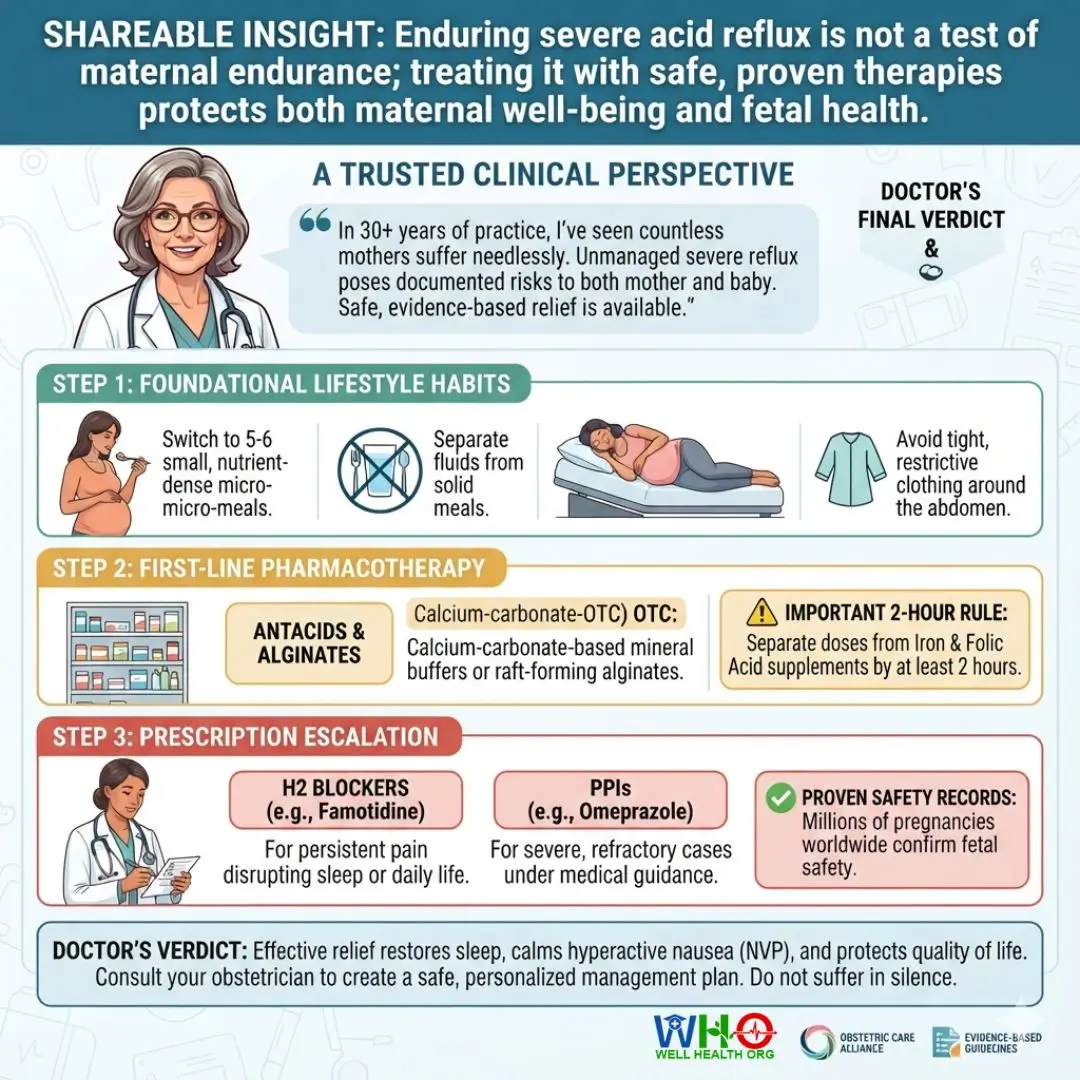
In my 30+ years of clinical practice, I have watched countless expecting mothers suffer needlessly through severe, debilitating gastroesophageal reflux because they feared that taking medication would harm their child. This is a profound and damaging misconception. The physiological stress of severe, unmanaged pain—marked by insomnia, poor nutrition, constant retching, elevated maternal cortisol, and systemic exhaustion—poses clear, documented risks to both mother and baby.
Maternal pyrosis and acid regurgitation during pregnancy are driven by powerful biological factors: progesterone-induced valve relaxation, delayed stomach emptying, and physical compression from the growing uterus. It is not an imaginary complaint, nor is it a personal failure of diet. Evidence-based medicine provides a clear, reliable path forward.
Begin with sound physiological habits: separate your fluids from solid meals, switch to five or six small, nutrient-dense micro-meals throughout the day, sleep on your left side with your bed elevated on an incline, and avoid wearing tight, restrictive clothing around your abdomen.
If symptoms persist past these lifestyle adjustments, step up treatment without hesitation. Start with calcium-carbonate-based mineral antacids or raft-forming alginates, taking care to space them two hours away from your iron and folic acid vitamins. If pain continues to disrupt your days or wake you from sleep, escalate under medical guidance to an H2 blocker like famotidine, or a proton pump inhibitor like omeprazole. The safety records for these medications across millions of pregnancies worldwide are clear and reassuring. Relieving your heartburn is a clinical necessity that restores your sleep, calms hyperactive nausea, and protects your quality of life during this crucial journey.
🌍 Geographic and Cultural Adaptation Strategies
🇺🇸 🇬🇧 🇪🇺 Western Clinical Guidelines & Lifestyle Management (US, UK, & Europe)
In high-income Western healthcare systems (such as the UK National Health Service, US obstetrics clinics, and European health systems), management of gestational reflux is guided by the National Institute for Health and Care Excellence (NICE) and American College of Obstetricians and Gynecologists (ACOG) guidelines.
- Over-the-Counter Formulations: Calcium carbonate chewables (e.g., Tums) are widely available first-line treatments across the US, while alginate-rich liquid suspensions (e.g., Gaviscon Advance containing sodium alginate and potassium bicarbonate) are standard across the UK and Europe. When purchasing alginates, ensure formulas are low in sodium and free of aluminum if used daily.
- Dietary Adjustments: Eliminate common hidden triggers common in Western diets, such as carbonated sodas, decaffeinated or caffeinated drip coffees, acidic citrus juices, concentrated tomato pastes (marinara sauces), and processed chocolate. Watch out for mint-flavored confectionery, which directly lowers esophageal valve pressure.
- Medical Support: Should simple antacids prove insufficient, UK and European physicians frequently prescribe famotidine 20 mg twice daily through primary care. US practitioners often escalate severe, erosive pyrosis to omeprazole 20 mg capsules taken 30 minutes before breakfast.
🇮🇳 🇵🇰 🇧🇩 🇸🇬 Asian Clinical Guidelines & Lifestyle Management (South & East Asia)
In South Asian, East Asian, and Southeast Asian clinical contexts, dietary patterns require specific cultural adjustments to protect the lower esophageal sphincter without sacrificing maternal nutrition.
- Managing Cooking Spices: Avoid hot capsaicin-heavy red chili powders, green chilies, whole mustard seeds, and sour tamarind concentrates. Replace them with gut-friendly aromatic carminatives like lightly boiled cumin seed (jeera) water, fresh ginger infusions in modest amounts, and crushed fennel seeds (saunf), which calm stomach spasms without irritating the esophageal lining.
- Modifying Cooking Oils: Avoid foods cooked with high amounts of clarified butter (ghee), heavy mustard oils, or deep-fried street snacks (such as samosas and pakoras). These heavy fats slow down stomach emptying and trigger hours of acid reflux. Switch to light stir-frying or boiling techniques using small amounts of heart-healthy oils.
- Safe Domestic Remedies: Use small amounts of unsweetened, diluted lassi made from homemade fresh yogurt (curd) containing active probiotics, or drink tender coconut water during morning hours to soothe stomach burning. Avoid taking unregulated Ayurvedic or traditional herbal powders (churan), as many contain very high levels of hidden sodium bicarbonate or unrefined salts that can dangerously elevate blood pressure.
7. Global Frequently Asked Questions (Maternal GERD)
Does severe heartburn in pregnancy mean my baby will be born with a full head of hair?
Is it safe to drink baking soda mixed with water to calm severe heartburn?
- It quickly absorbs into your bloodstream, introducing a sudden alkaline load that can trigger metabolic alkalosis in both mother and baby.
- It contains high levels of sodium, which pulls water into your vascular system. This can worsen fluid retention, provoke peripheral edema, and cause blood pressure spikes in women at risk for gestational hypertension or pre-eclampsia.
Instead, choose doctor-approved calcium carbonate chewable tablets or safe alginate oral suspensions.
Can taking antacids stop my body from absorbing my prenatal vitamins and iron?
Why does my heartburn feel so much worse when I lie flat on my back?
Are Proton Pump Inhibitors (PPIs) like omeprazole safe during the first trimester?
When does pregnancy-related acid reflux typically disappear after delivery?
Medically Reviewed by Prof. Dr. Akram
Orthopedic Surgeon | Professor | Senior Medical Specialist
Prof. Dr. Akram is a distinguished surgeon with over 15 years of clinical expertise. Having served as a lead Emergency Specialist at Complex International Government Hospital, he currently leads a specialized team of 13 medical professionals at his private hospital. As a Professor at top medical universities, he ensures that every article on WellHealthOrg.com meets rigorous clinical standards.
Medical Disclaimer:
The information provided is for educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult your physician for any medical concerns.
Our content is rigorously fact-checked by our 13-member Editorial Team under the clinical supervision of Prof. Dr. Akram.







