

🩺 Dr. Akram’s Private Clinical Notes for Natural Treatment for Swollen Ankles and Feet
“In my thirty-two years of bedside practice across tertiary centers in London, Dubai, and Singapore, I have evaluated thousands of patients presenting with swollen lower limbs. I recall Marcus, a 54-year-old financial director from Frankfurt, who flew regularly across continents. He arrived at my clinic with calves so distended and tight that his socks left deep, purple indentations into his periosteum. He feared he had intractable kidney failure. Conversely, I remember Meera, a 61-year-old schoolteacher from Chennai, who spent eight hours daily on hard concrete floors amidst tropical humidity, her ankles ballooning by mid-afternoon until walking became agony.
Both presented with what modern medicine categorizes broadly as peripheral edema, yet their underlying physiological triggers were strikingly distinct. Marcus suffered from prolonged mechanical capillary pooling and high dietary restaurant sodium, while Meera suffered from early venous valvular incompetence combined with subclinical electrolyte imbalances. Swelling in the ankles and feet is rarely a standalone disease. It is a biological alarm system—a signal that the delicate microvascular equilibrium governing fluid exchange between blood vessels, lymphatic ducts, and interstitial tissues has collapsed under mechanical or biochemical stress. Once we understand this fluid architecture, resolving it becomes a matter of physiological precision rather than guesswork.”
What is Swollen Ankles and Feet (Peripheral Edema)?
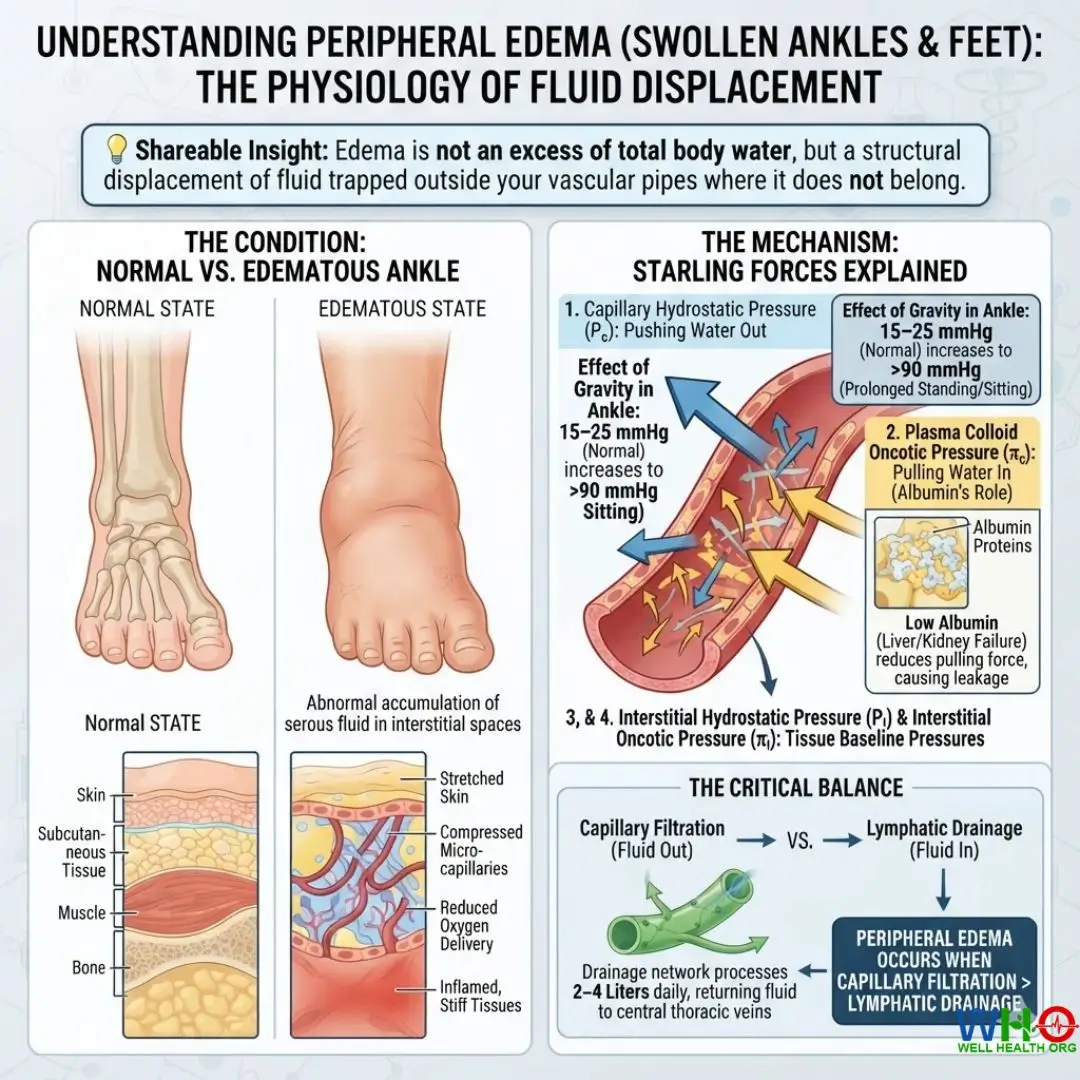
In simple medical terms, swollen ankles and feet—known clinically as dependent peripheral edema—represent an abnormal accumulation of serous fluid within the interstitial tissue spaces of the lower extremities. The human body is approximately sixty percent water, compartmentalized into intracellular spaces (inside your cells), intravascular spaces (inside your blood vessels and arteries), and interstitial spaces (the microscopic gel-like gaps surrounding cells, muscles, and nerves). Under normal biological circumstances, fluid moves dynamically across these compartments to deliver oxygen and nutrients before returning safely into circulation.
When this delicate transport network breaks down, gravity pulls fluid down to your lowest anatomical regions: the feet, ankles, and distal calves. This is not simply a cosmetic annoyance. When fluid pools in your ankles, your skin stretches, micro-capillaries are compressed, local oxygen delivery plummets, and tissues become inflamed, stiff, and prone to breakdown. To reverse this, we must look deeper than the surface of the skin.
The Microvascular Architecture: Starling Forces Explained
To understand why your feet swell, one must understand the physiology first discovered by the great physiologist Ernest Starling in 1896. Fluid movement across every single capillary in your body is dictated by a perpetual tug-of-war between two physical forces:
- Capillary Hydrostatic Pressure ($P_c$): The physical water pressure of blood pushing outwards against the vessel wall. When you stand or sit for prolonged periods, gravity increases hydrostatic pressure in your ankle veins from a normal 15–25 mmHg to over 90 mmHg. This outward pressure forces water straight through the semi-permeable capillary walls into the tissue spaces.
- Plasma Colloid Oncotic Pressure ($\Pi_c$): The pulling force generated primarily by circulating proteins, notably serum albumin. Albumin acts like a biological sponge, holding water inside your bloodstream. If your liver fails to produce enough albumin, or if your kidneys leak albumin into your urine, this pulling force drops, allowing fluid to spill freely into the surrounding tissue.
- Interstitial Hydrostatic Pressure ($P_i$) and Interstitial Oncotic Pressure ($\Pi_i$): The baseline pressures within the tissues themselves. When lymphatic channels become clogged or damaged, tissue protein levels climb, pulling even more fluid out of the blood vessels.
Under ordinary health, whatever microscopic fluid escapes into the tissues is swiftly collected by your lymphatic system—a drainage network processing two to four liters of fluid daily—and returned directly to your central thoracic veins. Peripheral edema occurs the moment capillary filtration outpaces lymphatic drainage.
Clinical Differentiation: Pitting vs. Non-Pitting Edema
When patients visit my practice, the very first test I perform is simple: I press my thumb firmly over their anterior tibia (shin bone) or medial malleolus (inner ankle) for a full five to ten seconds, then release. What happens next reveals the underlying pathology:
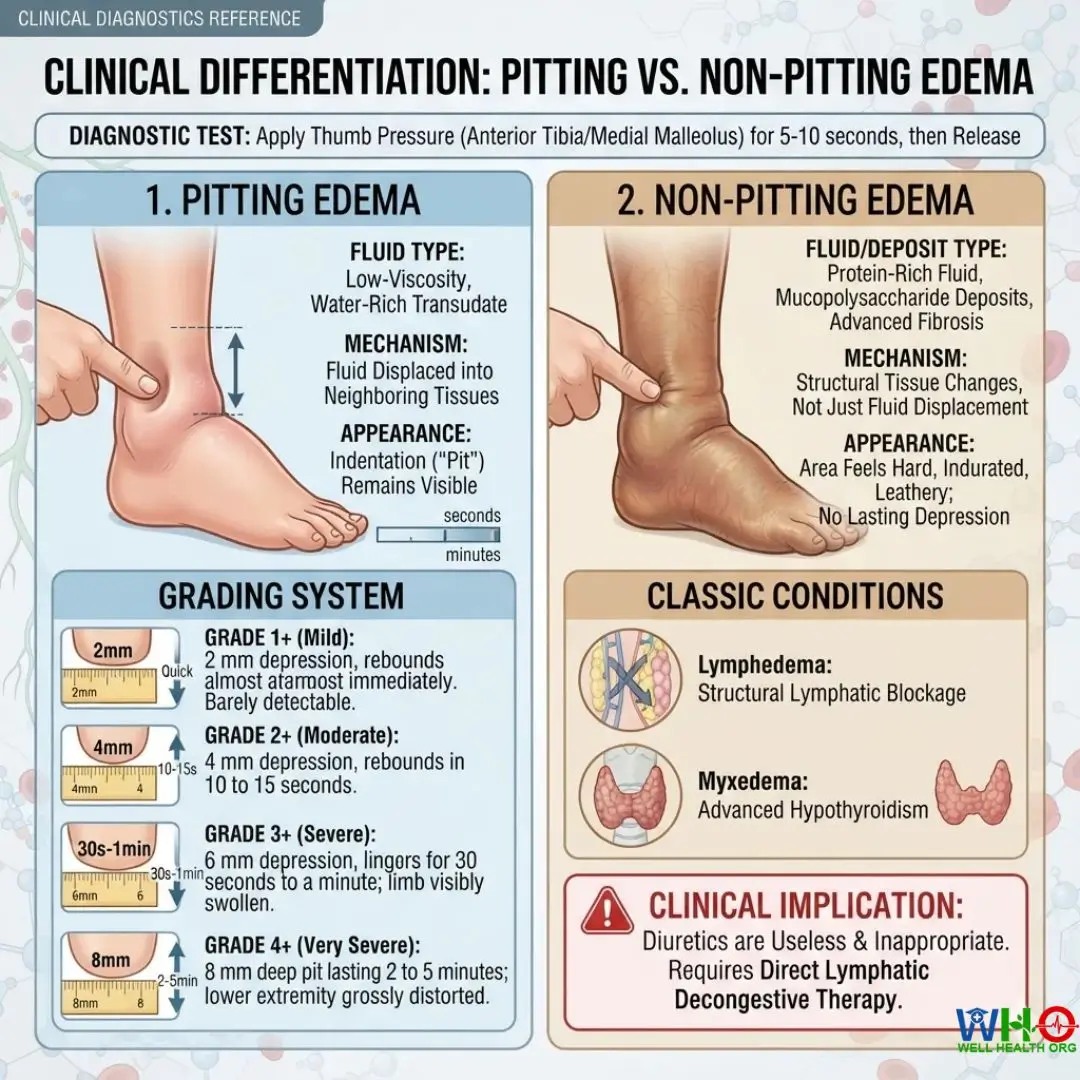
1. Pitting Edema: If releasing your thumb leaves an indentation or “pit” that remains visible for seconds or minutes, you are dealing with pitting edema. This indicates low-viscosity, water-rich transudate fluid that has been displaced into neighboring tissues. Pitting edema is typically graded clinically:
- Grade 1+ (Mild): 2 mm depression that rebounds almost immediately. Barely detectable.
- Grade 2+ (Moderate): 4 mm depression that rebounds in 10 to 15 seconds.
- Grade 3+ (Severe): 6 mm depression that lingers for 30 seconds to a minute; limb visibly swollen.
- Grade 4+ (Very Severe): 8 mm deep pit lasting 2 to 5 minutes; lower extremity grossly distorted.
2. Non-Pitting Edema: If the swollen area feels hard, indurated, or leathery, and your thumb leaves no lasting depression, this points toward protein-rich fluid, mucopolysaccharide deposits, or advanced structural fibrosis. This presentation is classic for lymphedema (structural lymphatic blockage) or myxedema (advanced hypothyroidism). Applying diuretic pills to non-pitting lymphedema is useless and clinically inappropriate; it demands direct lymphatic decongestive therapy.
The Root Causes: Global Lifestyles, Hemodynamics, and Diets
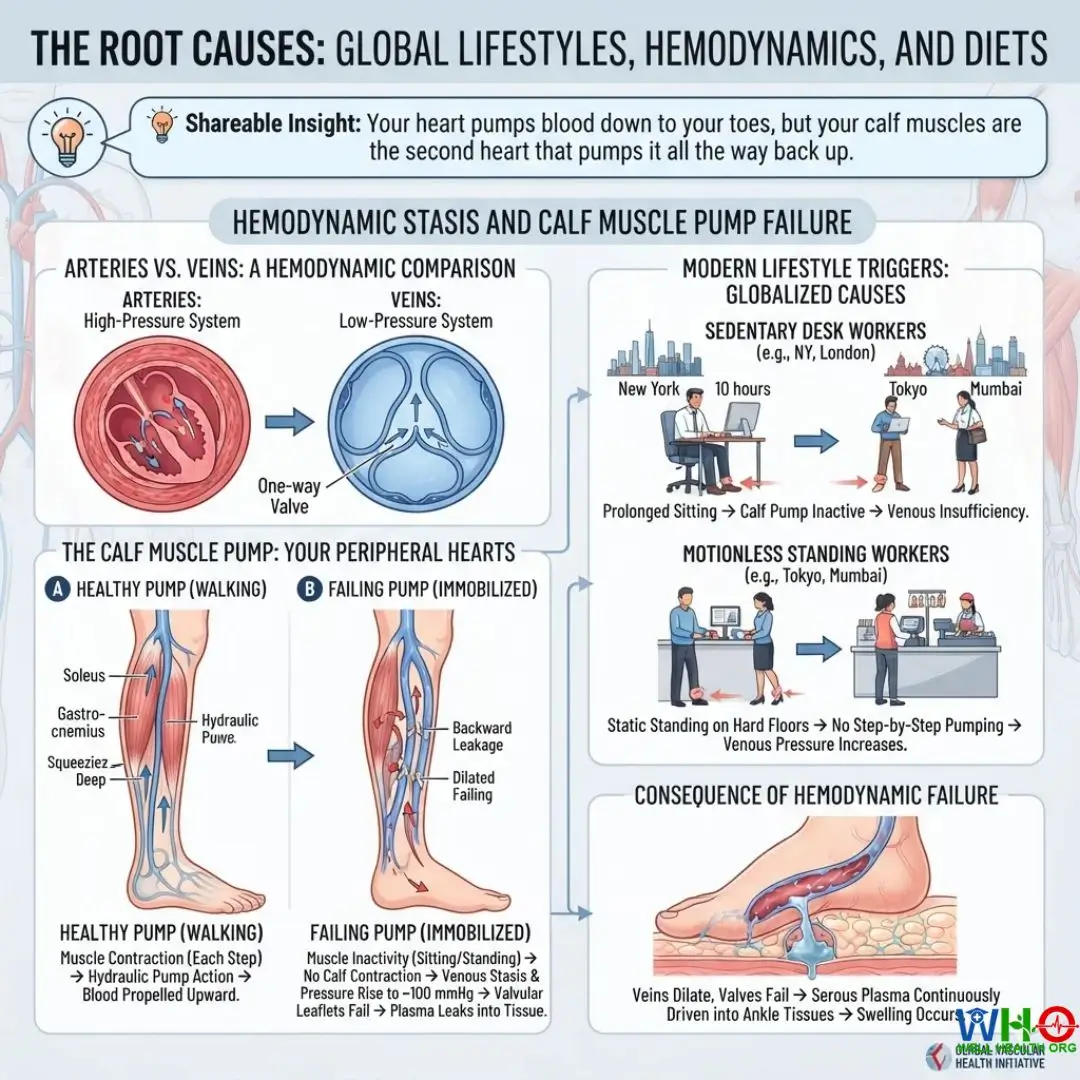
Swelling in the feet does not occur by accident. It is always an outcome of mechanical forces, systemic organ strain, or biochemical toxicity. In our modern globalized world, people living in New York, London, Tokyo, and Mumbai experience different physiological triggers based on lifestyle habits, workplace postures, and dietary traditions.
Hemodynamic Stasis and Calf Muscle Pump Failure
Unlike arteries, which have thick muscular walls that pulse blood forward under high pressure from the left ventricle, veins are thin-walled, compliant vessels operating under low pressure. Veins inside your legs rely on one-way bicuspid valves that prevent blood from falling backward toward your feet.
To propel deoxygenated blood back up against gravity, your body relies on the peripheral heart: the soleus and gastrocnemius muscles of the calf. Every time you take a step, these calf muscles contract, squeezing the deep veins like a hydraulic pump and shooting blood upward toward the inferior vena cava.
When modern knowledge workers sit immobilized at computer desks for ten hours, or retail and factory workers stand motionless on hard floors, this calf pump stops firing completely. Venous pressure in the ankle rises toward 100 mmHg, veins dilate, delicate valvular leaflets fail to meet (venous insufficiency), and serous plasma is continuously driven into your ankle tissues.
Systemic Pathologies: Cardiac, Renal, and Hepatic Drivers
When bilateral swelling (swelling in both feet equally) appears suddenly or worsens progressively, we must examine systemic organs:
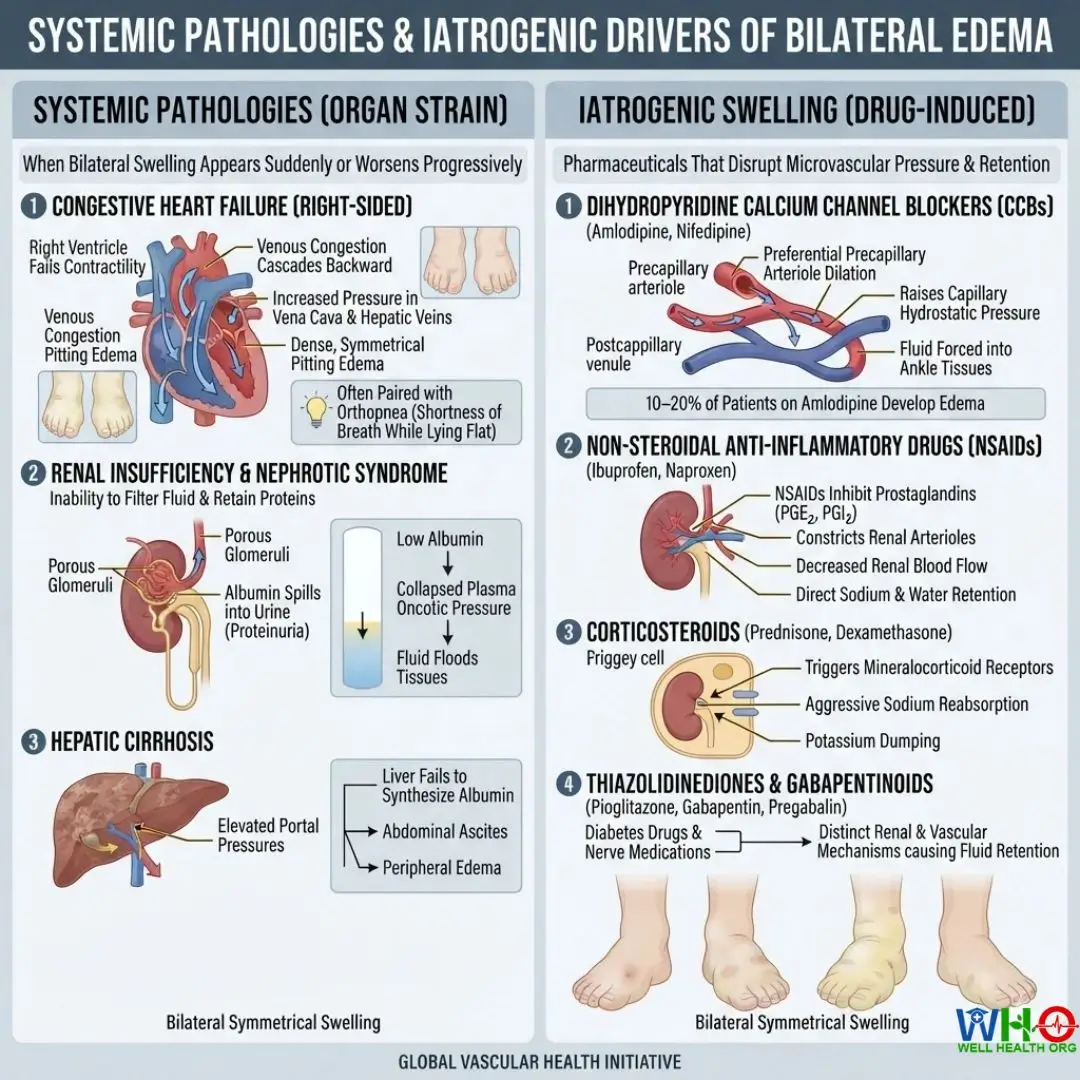
- Congestive Heart Failure (Right-Sided): When the right ventricle loses its pumping contractility, it cannot accommodate venous return. Blood backs up into the superior and inferior vena cava, cascading backward into the hepatic veins and lower extremities. This results in dense, bilateral, symmetrical pitting edema, often paired with shortness of breath while lying flat (orthopnea).
- Renal Insufficiency & Nephrotic Syndrome: Healthy kidneys filter fluid and retain essential proteins. In conditions like diabetic nephropathy or glomerulonephritis, the renal glomeruli become porous, allowing massive amounts of albumin to spill into the urine (proteinuria). Without albumin, plasma oncotic pressure collapses, and fluid floods the tissues. Simultaneously, failing kidneys hold onto sodium, causing massive full-body fluid expansion.
- Hepatic Cirrhosis: Advanced liver scarring obstructs blood traveling from the intestines through the portal vein, elevating portal pressures. At the same time, the damaged liver loses its ability to synthesize albumin. This drives both abdominal ascites (fluid in the belly) and lower extremity edema.
Iatrogenic Swelling: Pharmaceuticals That Trigger Retention
Frequently in my practice, a patient’s “incurable” swollen feet are caused by their daily prescription medications. Many common drugs deliberately or accidentally disrupt microvascular pressure gradients:
- Dihydropyridine Calcium Channel Blockers (Amlodipine, Nifedipine): Widely prescribed for high blood pressure, these drugs dilate precapillary arterioles far more than postcapillary venules. This physiological mismatch raises hydrostatic pressure directly within the capillary bed, forcing fluid into ankle tissues. Between 10% and 20% of patients taking 10 mg of amlodipine develop significant peripheral edema within months.
- Non-Steroidal Anti-Inflammatory Drugs (NSAIDs: Ibuprofen, Naproxen, Diclofenac): Frequent use inhibits renal prostaglandins ($PGE_2$ and $PGI_2$), leading to constriction of renal arterioles, decreased blood flow to the kidneys, and direct sodium and water retention.
- Corticosteroids (Prednisone, Dexamethasone): These medications trigger mineralocorticoid receptors, instructing the kidneys to aggressively reabsorb sodium while dumping potassium.
- Thiazolidinediones & Gabapentinoids: Diabetes drugs like pioglitazone and nerve medications like gabapentin or pregabalin frequently cause fluid retention through distinct renal and vascular mechanisms.
Western Ultra-Processed Diets vs. Eastern High-Sodium Seasonings
Dietary drivers of peripheral edema vary significantly across global populations, but all share a common denominator: an imbalance between sodium and potassium.
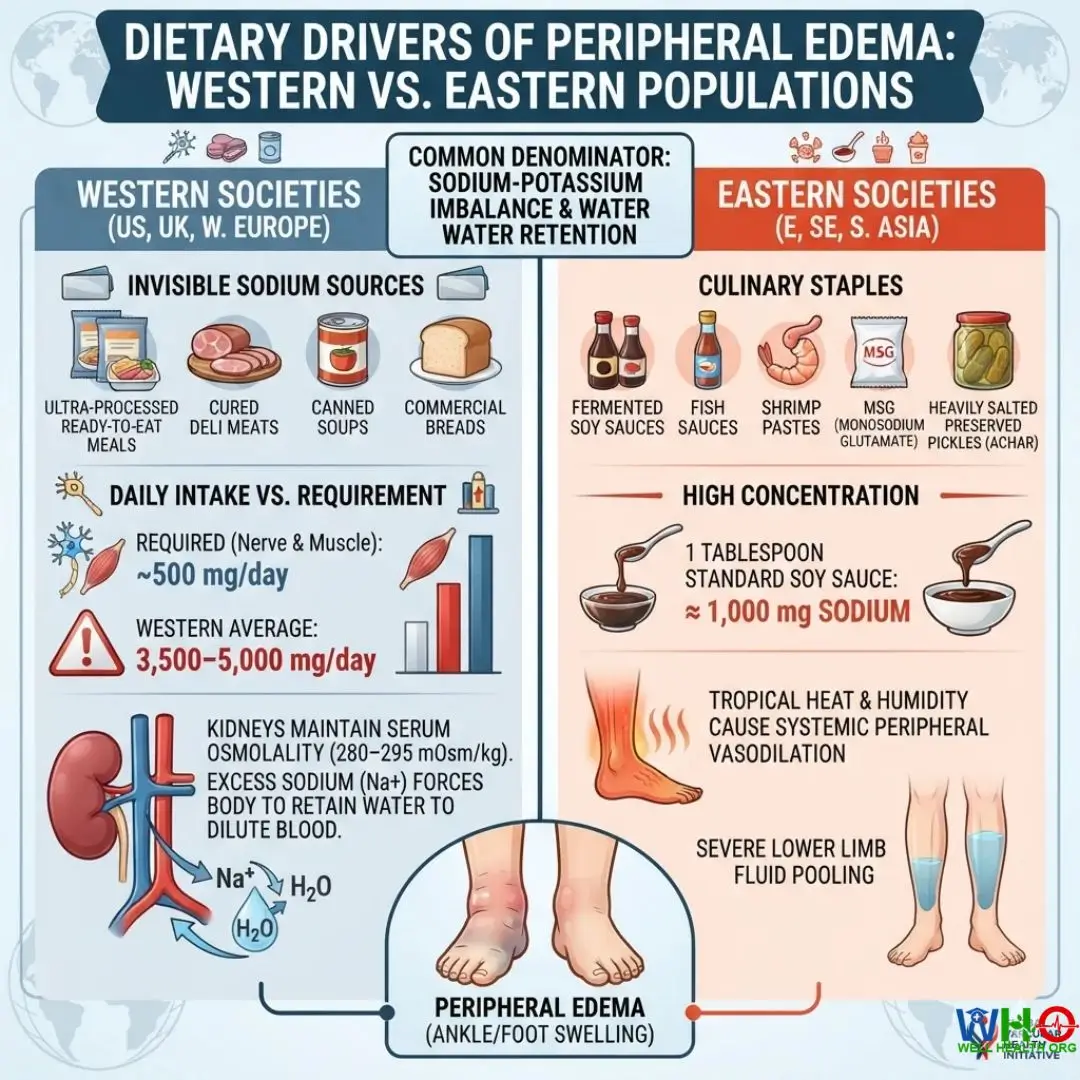
In Western societies (the United States, United Kingdom, and Western Europe), excessive sodium intake stems largely from invisible sources: ultra-processed ready-to-eat meals, cured deli meats, canned soups, and commercial breads. The human body requires roughly 500 mg of sodium per day for nerve conduction and muscular balance; the average Western diet delivers 3,500 to 5,000 mg daily. Because the kidneys must maintain tight blood serum osmolality (roughly 280–295 mOsm/kg), every excess molecule of sodium forces the body to retain additional water to dilute it.
In Eastern societies (East, Southeast, and South Asia), the culprit is rarely packaged Western junk food, but rather hyper-concentrated culinary staples: fermented soy sauces, fish sauces, shrimp pastes, monosodium glutamate (MSG), and heavily salted preserved pickles (achar). A single tablespoon of standard commercial soy sauce carries nearly 1,000 mg of sodium. When consumed in regions with high tropical heat and humidity—which causes systemic peripheral vasodilation—the physiological consequence is severe lower limb fluid pooling.
Advanced Medical Treatments and Pharmacological Approaches
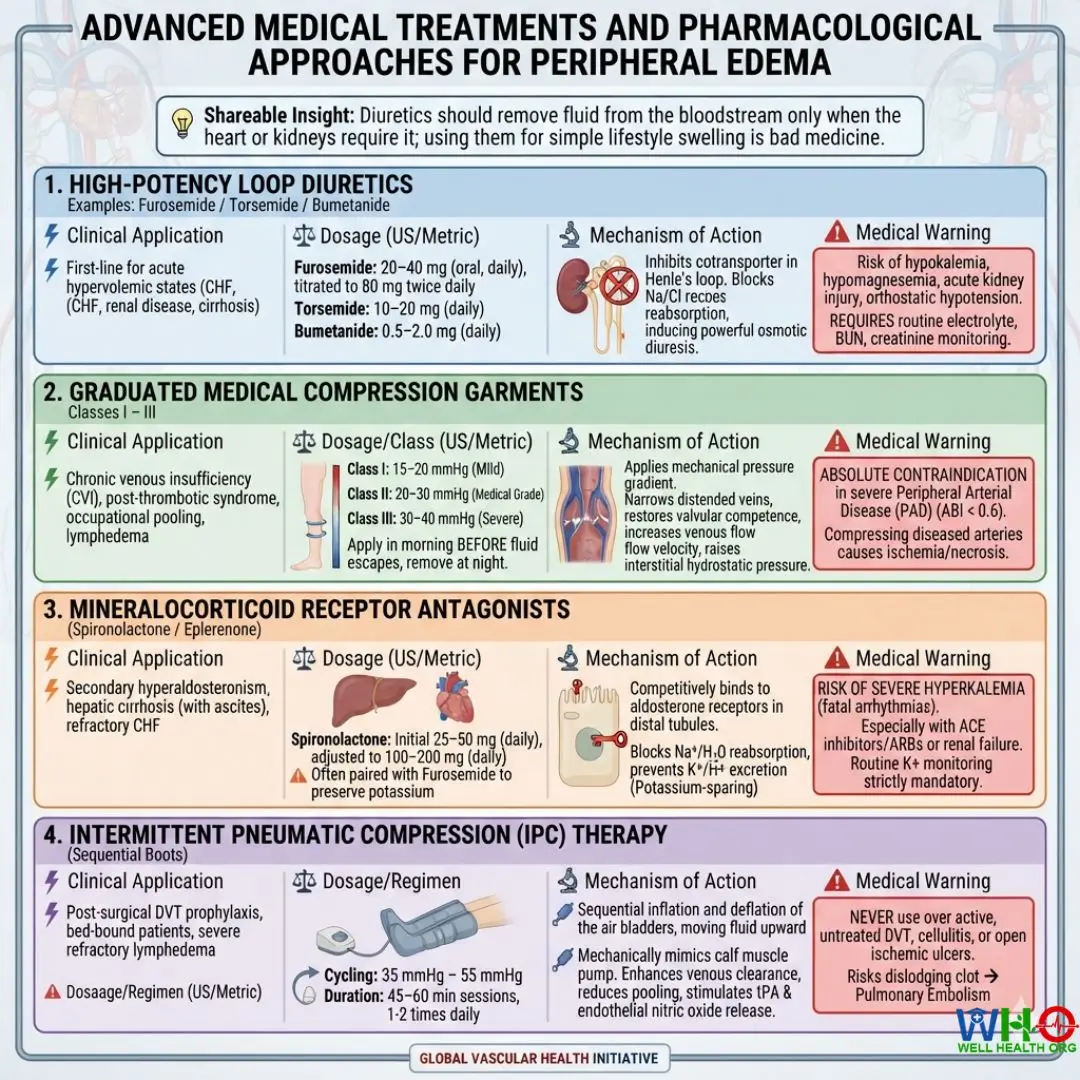
When home-based measures are insufficient or the patient suffers from underlying structural organ failure, advanced clinical medicine steps in. Below are the standard, evidence-based therapies utilized in modern vascular and internal medicine wards worldwide.
High-Potency Loop Diuretics (Furosemide / Torsemide / Bumetanide)
⚡ Clinical Application: First-line pharmacotherapy for acute hypervolemic states driven by congestive heart failure, renal disease, or cirrhosis with peripheral fluid retention. Not indicated for simple mechanical dependent stasis.
⚖️ Dosage (US/Metric): Furosemide: 20 mg to 40 mg orally once daily, titrated upward to 80 mg twice daily based on clinical response. Torsemide: 10 mg to 20 mg orally once daily (provides more reliable bioavailability). Bumetanide: 0.5 mg to 2.0 mg daily.
🔬 Mechanism of Action: Reversibly inhibits the $Na^+/K^+/2Cl^-$ cotransporter protein located in the thick ascending limb of the Henle’s loop in the kidney. This prevents sodium and chloride reabsorption, inducing rapid, powerful osmotic diuresis (water excretion in the urine) and reducing intravascular volume and hydrostatic pressure.
⚠️ Medical Warning: Risk of profound hypokalemia (potassium depletion), severe hypomagnesemia, acute kidney injury via prerenal azotemia, and symptomatic orthostatic hypotension. Serum electrolytes, blood urea nitrogen (BUN), and creatinine must be monitored regularly via blood panels.
Graduated Medical Compression Garments (Class I – Class III)
⚡ Clinical Application: Standard management for chronic venous insufficiency (CVI), post-thrombotic syndrome, occupational orthostatic pooling, and stage I/II secondary lymphedema.
⚖️ Dosage (US/Metric): Class I (Mild Over-the-Counter): 15–20 mmHg; Class II (Medical Grade Prescribed): 20–30 mmHg; Class III (Severe Venous Stasis/Lymphedema): 30–40 mmHg. Must be applied early in the morning before fluid leaves the vascular bed and removed at night.
🔬 Mechanism of Action: Applies a mechanical pressure gradient that is tightest at the ankle and gradually loosens as it travels up the calf. This narrows the diameter of distended deep veins, restores competent coaptation of venous valves, increases linear venous flow velocity, and raises interstitial hydrostatic pressure to prevent fluid from escaping the capillaries.
⚠️ Medical Warning: Absolute contraindication in patients with severe Peripheral Arterial Disease (PAD) (defined as an Ankle-Brachial Index [ABI] < 0.6). Compressing diseased arteries can induce critical lower extremity ischemia, necrosis, and tissue death.
Mineralocorticoid Receptor Antagonists (Spironolactone / Eplerenone)
⚡ Clinical Application: Specifically tailored for secondary hyperaldosteronism, hepatic cirrhosis accompanied by lower limb edema and ascites, and refractory congestive heart failure.
⚖️ Dosage (US/Metric): Spironolactone: Initial dose of 25 mg to 50 mg orally once daily, adjusted up to 100 mg–200 mg daily in cirrhotic protocols (often paired alongside Furosemide in a 100mg:40mg ratio to preserve serum potassium balance).
🔬 Mechanism of Action: Competitively binds to aldosterone receptors in the late distal renal tubules and collecting ducts. It blocks the reabsorption of sodium and water while preventing the urinary excretion of potassium and hydrogen ions.
⚠️ Medical Warning: Dangerous risk of severe hyperkalemia (fatal cardiac arrhythmias), particularly when administered alongside ACE inhibitors, ARBs, or in the presence of underlying chronic renal failure. Routine serum potassium blood monitoring is strictly mandatory.
Intermittent Pneumatic Compression (IPC) Therapy
⚡ Clinical Application: Inpatient post-surgical deep vein thrombosis prophylaxis, bed-bound patients, and severe refractory peripheral lymphedema resistant to baseline stockings.
⚖️ Dosage (US/Metric): Automated sequential pneumatic boots cycling between 35 mmHg and 55 mmHg of pressure for 45 to 60-minute therapeutic sessions, 1 to 2 times daily.
🔬 Mechanism of Action: Mechanically inflates and deflates compartmental air bladders around the feet and calves sequentially, mimicking the physiological calf muscle pump. This dramatically enhances venous clearance, lowers venous pooling, and stimulates the release of endothelial nitric oxide and tissue plasminogen activator (tPA).
⚠️ Medical Warning: Never use over an active, untreated Deep Vein Thrombosis (DVT), infected cellulitis, or open ischemic leg ulcers. Doing so risks dislodging a blood clot directly into the pulmonary arteries, triggering a life-threatening pulmonary embolism.
Proven Natural Treatments and Home Remedies
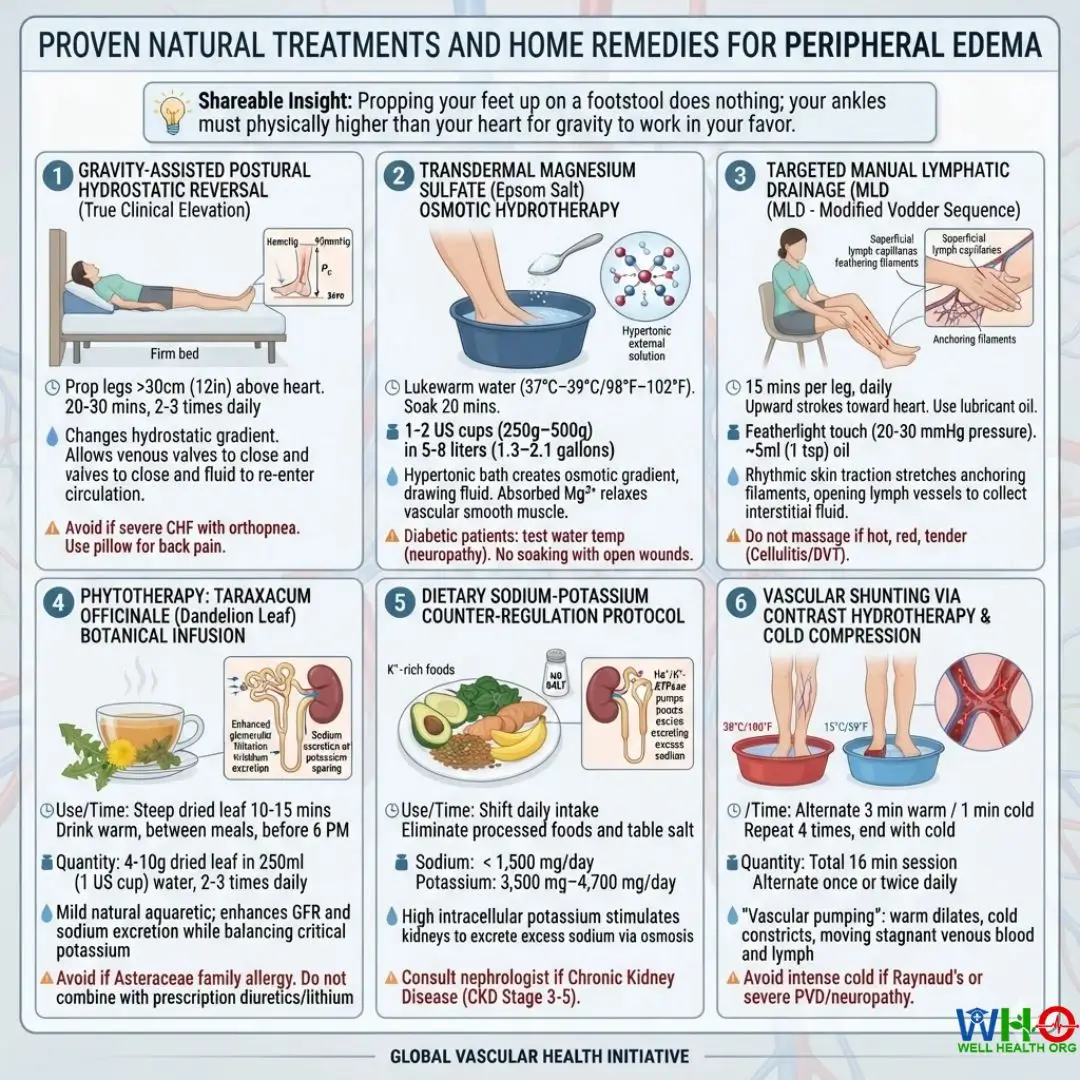
For the millions of individuals whose swelling stems from occupational immobility, long-distance flights, minor venous insufficiency, seasonal heat, or dietary sodium retention, pharmaceutical intervention is often unnecessary. Targeted natural and physical interventions—applied with clinical discipline—can rapidly restore fluid equilibrium.
Gravity-Assisted Postural Hydrostatic Reversal (True Clinical Elevation)
⚡ Preparation & Use: Lie flat on your back on a firm bed, yoga mat, or floor. Prop your legs up on a wedge pillow or flat against a wall (the restorative yoga “Viparita Karani” posture) so that your heels and ankles are elevated at least 30 centimeters (12 inches) above the anatomical level of your heart. Maintain this position undisturbed for 20 to 30 minutes, 2 to 3 times every day.
⚖️ Quantity (US/Metric): Minimum 30 degrees of leg incline; performed for 20–30 minutes per session.
🔬 Natural Healing Process: This maneuver changes the hydrostatic pressure gradient in the lower limbs. By placing the ankles above the right atrium of the heart, gravitational hydrostatic pressure ($P_c$) in the ankle microvasculature drops from roughly 90 mmHg to near zero. This allows the venous valves to close without backward pressure and lets trapped interstitial fluid flow freely back into the circulatory and lymphatic systems.
⚠️ Safe Usage Note: If you experience lower back pain or numbness in the legs, place a small pillow beneath your sacrum or slightly bend your knees. Avoid this posture if you have severe congestive heart failure and experience immediate shortness of breath when lying flat.
Transdermal Magnesium Sulfate (Epsom Salt) Osmotic Hydrotherapy
⚡ Preparation & Use: Fill a deep basin or foot bath with lukewarm water (ideally 37°C to 39°C / 98°F to 102°F—never hot). Fully dissolve high-grade Epsom salt into the water. Submerge both feet and ankles up to the lower calf for exactly 20 minutes. Pat dry thoroughly and moisturize immediately with an unperfumed cream to prevent skin cracking.
⚖️ Quantity (US/Metric): 1 to 2 standard US cups (approximately 250 g to 500 g) of pure magnesium sulfate heptahydrate dissolved in 5 to 8 liters (1.3 to 2.1 gallons) of water.
🔬 Natural Healing Process: The concentrated magnesium sulfate bath creates a mild hypertonic external solution, generating an osmotic gradient that helps draw fluid from swollen superficial layers. Simultaneously, absorbed magnesium ions relax vascular smooth muscle, improving micro-capillary circulation and easing inflammatory tension around swollen joints.
⚠️ Safe Usage Note: Diabetic patients must always test water temperature with their elbow first to prevent burns due to diabetic peripheral neuropathy. Never soak feet with active ulcers, weeping eczema, or open surgical wounds.
Targeted Manual Lymphatic Drainage (MLD – Modified Vodder Sequence)
⚡ Preparation & Use: Sit in an upright, supported position. Apply a thin layer of natural sweet almond or jojoba oil. Begin by lightly massaging the groin and behind the knees to clear central lymph nodes. Then, using flat palms and very light pressure (just enough to stretch the skin, not compress deep muscle), perform rhythmic upward sweeping strokes starting from the toes, over the ankles, and up toward the knee. Always stroke *upward* toward the heart; never massage down toward the toes.
⚖️ Quantity (US/Metric): Perform for 15 minutes per leg daily, using roughly 5 ml (1 teaspoon) of lubricant oil. Apply featherlight touch (roughly 20 to 30 mmHg of hand pressure).
🔬 Natural Healing Process: Superficial lymphatic capillaries sit directly beneath the epidermis, held in place by tiny anchoring filaments. Heavy, deep tissue massage crushes these delicate vessels. Very light, rhythmic skin traction stretches these filaments open, allowing trapped proteins and interstitial fluid to enter the lymphatic system and be routed toward the thoracic duct.
⚠️ Safe Usage Note: Do not massage if the leg is hot, red, or tender to the touch, as this may indicate cellulitis or an active blood clot (DVT). Massaging a clot can break it free, leading to a pulmonary embolism.
Phytotherapy: Taraxacum officinale (Dandelion Leaf) Botanical Infusion
⚡ Preparation & Use: Steep dried organic dandelion leaf (ensure you use the leaf, which has diuretic properties, rather than the root, which supports the liver) in boiling water for 10 to 15 minutes in a covered mug to preserve volatile oils. Strain and drink warm between meals. Consume the final cup of the day before 6:00 PM to avoid nighttime urination.
⚖️ Quantity (US/Metric): 4 to 10 grams of dried leaf steeped in 250 ml (1 US cup) of water, consumed 2 to 3 times daily.
🔬 Natural Healing Process: Dandelion leaf is one of the few botanicals shown to act as a mild, natural aquaretic by enhancing glomerular filtration and sodium excretion. Unlike pharmaceutical loop diuretics which deplete potassium, dandelion leaf contains natural potassium (nearly 4% dry weight), keeping this critical electrolyte balanced while encouraging excess fluid loss.
⚠️ Safe Usage Note: Avoid if you have an allergy to plants in the Asteraceae/Compositae family (ragweed, daisies). Do not combine with prescription diuretics (like furosemide or spironolactone) or lithium without physician guidance.
Dietary Sodium-Potassium Counter-Regulation Protocol
⚡ Preparation & Use: Shift your dietary intake to achieve a 3:1 potassium-to-sodium ratio. Reduce dietary sodium to under 1,500 mg daily by eliminating processed foods and table salt. Simultaneously, add potassium-dense whole foods to your daily meals: avocados, steamed spinach, sweet potatoes, coconut water, lentils, and bananas.
⚖️ Quantity (US/Metric): Sodium: < 1,500 mg per day. Potassium: 3,500 mg to 4,700 mg per day from whole-food sources.
🔬 Natural Healing Process: Potassium and sodium work together in a delicate balance. High intracellular potassium concentrations stimulate your kidneys’ $Na^+/K^+$-ATPase pumps to excrete excess sodium via the distal renal tubules. As sodium is excreted in your urine, it pulls excess water along with it through osmosis, lowering intravascular volume and relieving pressure in your lower limbs.
⚠️ Safe Usage Note: Individuals with Chronic Kidney Disease (CKD Stage 3–5) must not follow a high-potassium diet without direct nephrologist oversight. Failing kidneys struggle to clear potassium, which can lead to life-threatening hyperkalemia.
Vascular Shunting via Contrast Hydrotherapy & Cold Compression
⚡ Preparation & Use: Prepare two basins: Basin A filled with warm water (38°C / 100°F) and Basin B filled with cold water (15°C / 59°F). Submerge feet in warm water for 3 minutes, then instantly plunge into cold water for 1 minute. Alternate this cycle 4 times, always ending with the cold water immersion. Alternatively, apply an ice pack wrapped in a damp cotton towel around the ankles for 15 minutes.
⚖️ Quantity (US/Metric): 3 minutes warm to 1 minute cold, repeated across a total 16-minute session once or twice daily.
🔬 Natural Healing Process: Alternating temperatures produces what vascular clinicians term “vascular pumping.” Warm water dilates local capillaries, while cold water rapidly constricts them through sympathetic alpha-adrenergic pathways. This alternation acts as a mechanical pump that moves stagnant venous blood and accelerates lymphatic drainage without requiring intense muscular effort.
⚠️ Safe Usage Note: Avoid intense cold immersion if you have Raynaud’s phenomenon, severe peripheral vascular disease, or sensory peripheral neuropathy.
Critical Red Flags: When Swelling Signals a Medical Emergency
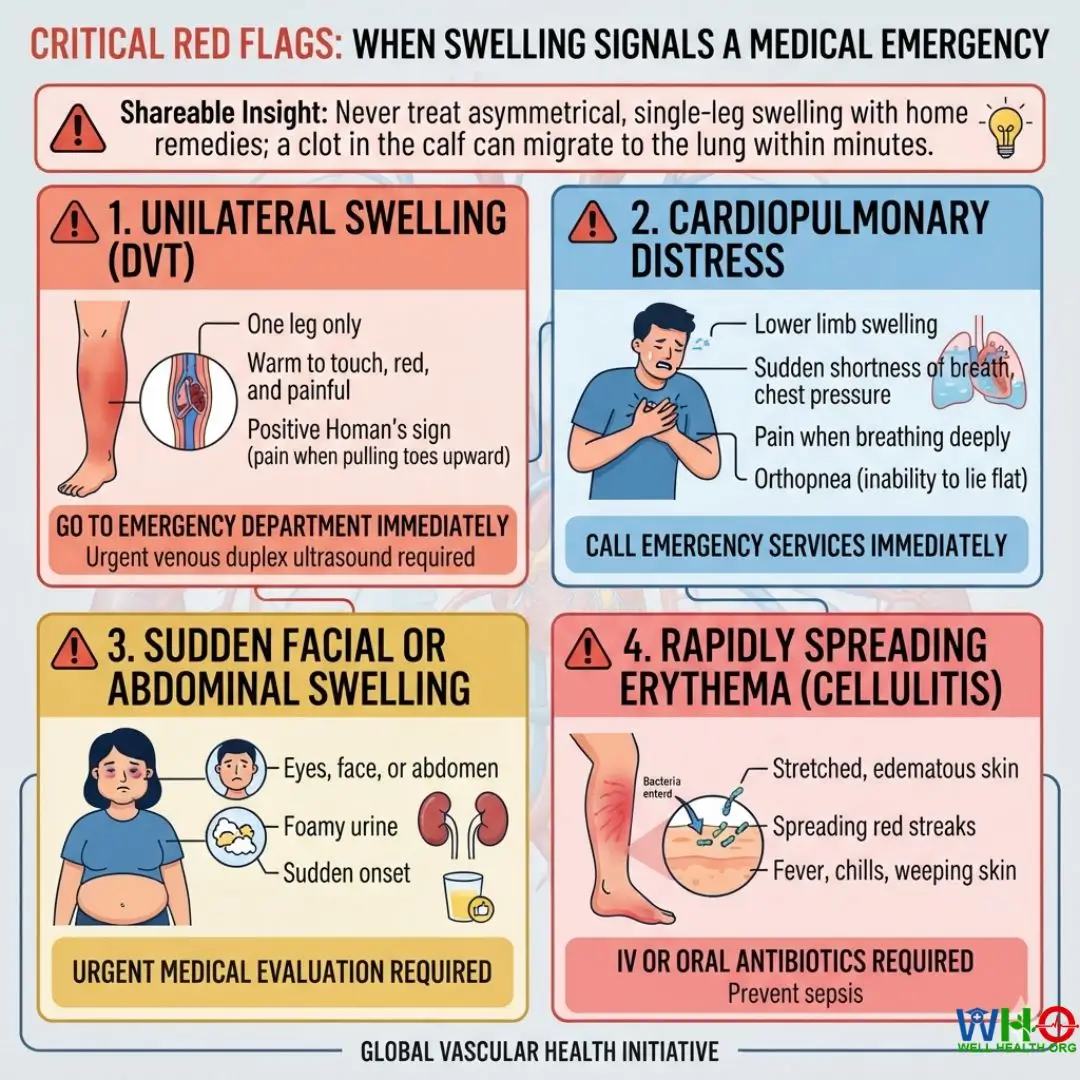
While most swollen ankles stem from everyday factors like prolonged sitting, dietary salt, or mild venous insufficiency, swelling can also be an early sign of a life-threatening medical emergency. It is critical to recognize these warning signs immediately:
🚨 Immediate Emergency Red Flag Criteria
- Unilateral Swelling (One Leg Only): If only one ankle or calf is swollen, warm to the touch, red, and painful—especially when pulling your toes upward toward your shin (positive Homan’s sign)—suspect a Deep Vein Thrombosis (DVT). A venous clot can dislodge and travel directly to the lungs, triggering a fatal pulmonary embolism. Proceed immediately to an emergency department for an urgent venous duplex ultrasound.
- Swelling Accompanied by Cardiopulmonary Distress: If lower limb swelling appears alongside sudden shortness of breath, chest pressure, pain when breathing deeply, or an inability to lie flat without suffocating (orthopnea), this signals acute left- and right-sided congestive heart failure with pulmonary edema. Call emergency services immediately.
- Sudden Onset Facial, Periorbital, or Abdominal Swelling: If swelling begins in the eyes, face, or abdomen alongside foamy urine, this points toward acute nephrotic syndrome or acute renal failure.
- Rapidly Spreading Erythema and Warmth (Cellulitis): Stretched, edematous skin can develop microscopic tears that let bacteria in. If the swelling is accompanied by spreading red streaks, fever, chills, or weeping skin, broad-spectrum intravenous or oral antibiotics are required to prevent sepsis.
Doctor’s Final Verdict & The Bottom Line
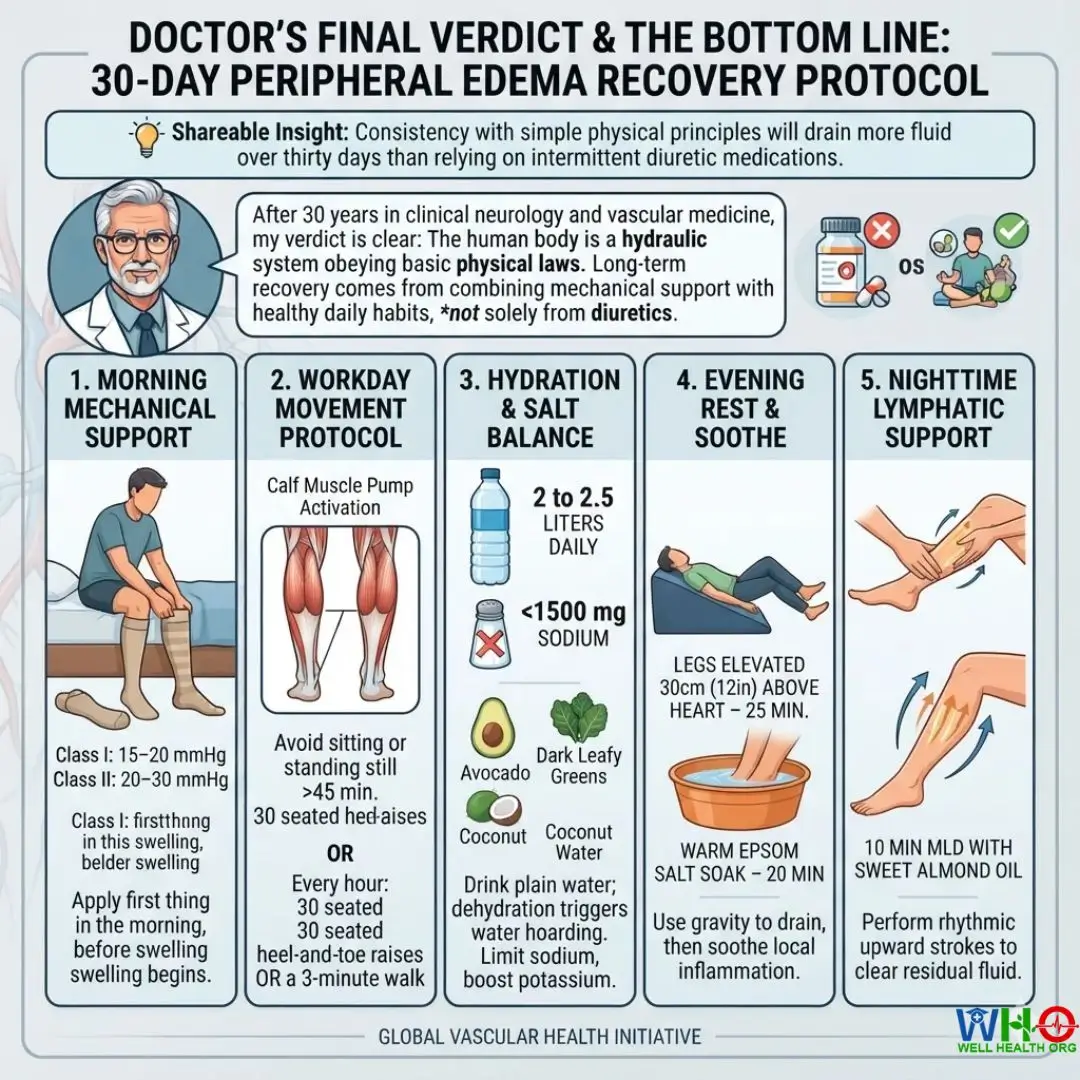
After three decades in clinical neurology and vascular medicine, my verdict is simple: the human body is a hydraulic system that obeys basic physical laws. Peripheral edema is rarely an unpredictable problem. It is usually the direct result of fluid physics working against modern lifestyles.
Relying solely on diuretic pills without addressing daily habits is poor medical strategy. Diuretics place unnecessary strain on kidney nephrons, deplete essential electrolytes, and can cause rebound fluid retention once stopped. The most reliable long-term recovery comes from combining mechanical support with healthy daily habits. Here is my practical, step-by-step recovery plan for non-emergency peripheral edema:
📋 The 30-Day Step-by-Step Recovery Protocol
- Morning Step: Put on Class I (15–20 mmHg) or Class II (20–30 mmHg) graduated compression socks first thing in the morning, while your feet are still drained from sleep. Do not wait until swelling begins at midday.
- Workday Movement: Avoid sitting or standing still for more than 45 minutes at a time. Every hour, perform 30 seated heel-and-toe raises or take a brief 3-minute walk to activate your calf muscle pump and keep fluid moving upward.
- Hydration & Salt Balance: Drink 2 to 2.5 liters of plain water daily. It sounds counterintuitive, but dehydration triggers aldosterone release, which instructs your kidneys to hoard water. Limit daily sodium to under 1,500 mg, and enjoy potassium-rich foods like avocados, dark leafy greens, and coconut water.
- Evening Routine: Lie down with your legs elevated 30 cm above your heart for 25 minutes. Follow this with a 20-minute Epsom salt soak (warm water, not hot) to soothe tired muscles and ease local inflammation.
- Nighttime Lymphatic Drainage: Spend 10 minutes gently stroking the legs upward toward the heart using sweet almond oil to help clear residual fluid into your central circulation.
Global Lifestyle Adaptations: Western vs. Eastern Populations
An effective clinical protocol must adapt to a patient’s everyday environment, diet, and climate. Below are targeted guidelines for Western and Eastern populations:
🌍 For Western Audiences: United States, United Kingdom & Europe
Primary Lifestyle Challenges: Prolonged sitting at desk-bound office jobs, long car commutes, heavily salted restaurant and ready meals, cold winter climates that discourage movement, and high consumption of carbonated soft drinks containing sodium benzoate.
Targeted Daily Steps:
- Desk Adjustments: Install an under-desk elliptical or pedal device, or switch to an electric sit-to-stand desk. Alternating between sitting and standing every 45 minutes activates the calf muscles and prevents fluid pooling.
- Sodium Management: Avoid the classic “hidden sodium” traps in Western supermarkets: sliced deli meats, packaged sandwich breads, canned pasta sauces, and frozen entrees. Check nutrition panels and aim for less than 140 mg of sodium per serving.
- Winter Hydration: Central home heating dries out the skin and respiratory tract, leading to unnoticeable dehydration that prompts the kidneys to hold onto water. Aim for 8 glasses of pure water or herbal teas daily; limit dehydrating lattes and alcohol.
- Travel Protocol: On flights longer than 3 hours, wear 15–20 mmHg knee-high compression stockings, avoid alcohol, and walk the aisle every 60 minutes.
🌏 For Eastern Audiences: South Asia, East Asia & Southeast Asia
Primary Lifestyle Challenges: High tropical heat and humidity causing peripheral vasodilation, occupations requiring prolonged static standing, cultural diets high in sodium-rich condiments (soy sauce, fish sauce, shrimp paste, achar, papadums), and lower intake of plain drinking water relative to sweating rates.
Targeted Daily Steps:
- Managing Tropical Heat: Intense heat naturally dilates peripheral blood vessels, causing blood to pool in the lower limbs. Counter this by keeping rooms well-ventilated, taking cool showers, and finishing with a 2-minute cold water rinse over the calves and feet.
- Condiment & Salt Substitutes: Replace traditional high-sodium sauces with fresh citrus (lemon, calamansi), fresh ginger, crushed garlic, raw turmeric, cumin, and coriander. These herbs add vibrant flavor and anti-inflammatory benefits without adding excess sodium. Limit papadums and preserved pickles to occasional treats.
- Natural Hydration: Enjoy fresh, natural tender coconut water daily. It is rich in potassium (roughly 600 mg per cup), helping the kidneys clear excess sodium. Avoid sugary bottled iced teas and milky drinks made with condensed milk.
- Workplace Habit: If you work on concrete or tile floors in retail, schools, or markets, avoid standing completely motionless. Shift weight from one leg to the other, alternate lifting your heels, and wear supportive, cushioned footwear with light, breathable compression socks.
Global Frequently Asked Questions (Clinical Answers)
Will drinking less water reduce the swelling in my feet and ankles?
No—in fact, it often does the exact opposite. Restricting water intake when you have uncomplicated lifestyle edema signals your body that it is entering a period of dehydration. In response, your pituitary gland secretes Antidiuretic Hormone (ADH / Vasopressin), and your adrenal glands release Aldosterone.
These hormones instruct your kidneys to reabsorb as much sodium and water as possible, worsening tissue fluid retention. Drinking sufficient water (2 to 2.5 liters daily) reassures your kidneys that fluids are plentiful, shutting down survival fluid hoarding and encouraging natural urination. (Note: If you have end-stage renal disease or severe congestive heart failure under strict medical fluid restrictions, always follow your cardiologist’s daily fluid limits.)
Why do my ankles only swell toward the end of the afternoon and evening?
This is classic orthostatic dependent edema. When you sleep at night, your body rests in a horizontal position. In this orientation, your lower extremities are level with your heart, eliminating gravitational hydrostatic pressure. Your veins and lymphatics can easily drain interstitial fluid back into the bloodstream, where your kidneys filter and excrete it—which is why your ankles are typically thinnest when you wake up.
Throughout the day, as you sit or stand, gravity continuously pulls fluid down into your feet, generating up to 90 mmHg of pressure in your ankle veins. If your calf muscle pump remains inactive, this pressure steadily forces fluid through your capillaries into surrounding tissues over 8 to 12 hours. By 5:00 PM, that accumulated fluid produces visible, palpable ankle swelling.
Can blood pressure medications like amlodipine cause swollen ankles?
Yes. Dihydropyridine calcium channel blockers (such as amlodipine, nifedipine, and felodipine) are a very common cause of peripheral edema.
These medications lower blood pressure by relaxing the smooth muscle walls of your arteries and precapillary arterioles. However, they have little dilating effect on postcapillary venules. This mismatch creates a bottleneck: blood flows rapidly into the capillaries but cannot exit with equal ease. Hydrostatic pressure inside the capillary spikes, forcing fluid into your ankle tissues.
This type of swelling is not true full-body fluid overload, which is why diuretic pills rarely resolve it. If you suspect your medication is causing your edema, speak with your physician. Adding an ACE inhibitor or ARB can help balance venous dilation, or your doctor may adjust your dosage or choose an alternative medication. Never stop taking blood pressure medications abruptly without medical guidance.
Is walking helpful or harmful for swollen ankles?
For simple dependent edema and mild venous insufficiency, walking is one of the most effective natural treatments available.
Standing motionless allows fluid to pool, but walking rhythmically flexes the soleus and gastrocnemius muscles in your calves. This acts as a natural pump that compresses deep veins, forces venous valves open, and propels stagnant fluid upward toward your heart.
The only exceptions: If your ankle swelling stems from an acute sprain, joint trauma, a suspected blood clot (DVT), an active skin infection (cellulitis), or if walking causes chest pain or shortness of breath. In those scenarios, stop walking immediately and seek a professional medical evaluation.
How can I tell the difference between venous edema and true lymphedema?
Clinicians use several key physical signs to distinguish between the two:
- Pitting Characteristics: Venous edema is typically soft, easily leaves an indentation when pressed (pitting), and improves significantly after a night of elevating your legs. Lymphedema often feels firm, rubbery, or thickened, and does not pit easily in later stages.
- Stemmer’s Sign: Try pinching a fold of skin at the base of your second toe. If you can easily pinch and lift the skin, Stemmer’s sign is negative (suggestive of venous edema). If the tissue is so thick and swollen that you cannot pinch it, the sign is positive, which is a classic indicator of lymphedema.
- Toe Involvement: Lymphedema typically causes swelling across the tops of the toes, giving them a squared-off look. Venous edema usually spares the toes and concentrates around the ankles and shins.
Medically Reviewed by Prof. Dr. Akram
Orthopedic Surgeon | Professor | Senior Medical Specialist
Prof. Dr. Akram is a distinguished surgeon with over 15 years of clinical expertise. Having served as a lead Emergency Specialist at Complex International Government Hospital, he currently leads a specialized team of 13 medical professionals at his private hospital. As a Professor at top medical universities, he ensures that every article on WellHealthOrg.com meets rigorous clinical standards.
Medical Disclaimer:
The information provided is for educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult your physician for any medical concerns.
Our content is rigorously fact-checked by our 13-member Editorial Team under the clinical supervision of Prof. Dr. Akram.







